

 PDF下载 ( 4226 KB)

原发性肝癌干预前并发心肌损伤的危险因素及列线图模型构建
DOI: 10.12449/JCH260919
Risk factors for concurrent myocardial injury before intervention in patients with primary hepatic carcinoma and construction of a nomogram prediction model
-
摘要:
目的 探讨原发性肝癌(PHC)患者干预前并发心肌损伤的独立危险因素,构建并验证可早期识别此类患者的列线图,为临床早期防治提供依据。 方法 回顾性收集2019年1月—2025年6月两所医疗机构1 822例PHC患者的临床资料,其中来自昆明市第三人民医院的1 518例作为训练集,用于构建模型;来自保山市第二人民医院的304例作为验证集。根据PHC患者干预前高灵敏度心肌肌钙蛋白T检测结果,将患者分为心肌损伤组和非心肌损伤组。采用单因素、LASSO回归及多因素Logistic回归分析PHC患者干预前并发心肌损伤的危险因素,并据此构建预测模型。通过304例验证集患者的独立数据进行外部验证,使用受试者操作特征曲线下面积(AUC)、Hosmer-Lemeshow拟合优度检验、校准曲线、临床决策曲线及临床影响曲线评价模型性能。 结果 训练集中,心肌损伤组346例,非心肌损伤组1 172例,并发心肌损伤患病率22.79%。年龄(56.44±9.45)岁、男性占81.49%、饮酒者占49.34%、吸烟者占57.44%、慢性乙型肝炎患者占61.73%、慢性丙型肝炎患者占32.48%、高血压者占22.66%、糖尿病者占17.19%、蔡尔德-皮尤分级A级者占50.53%、巴塞罗那肝癌临床分期B期者占33.86%、心电图异常者占62.12%。单因素、LASSO回归及多因素Logistic回归分析结果显示,年龄[比值比(OR)=1.051,95%置信区间(CI):1.036~1.067,P<0.001]、糖尿病史(OR=1.862,95%CI:1.346~2.574,P<0.001)、心电图(OR=1.446,95%CI:1.077~1.940,P=0.014)、血红蛋白(HGB)(OR=0.993,95%CI:0.988~0.998,P=0.003)、白蛋白(Alb)(OR=0.951,95%CI:0.930~0.972,P<0.001)、肌酐(Cr)(OR=1.021,95%CI:1.016~1.026,P<0.001)是PHC患者发生心肌损伤的独立影响因素,据此建立回归方程:Logit(Y)=-3.406+0.050×年龄+0.621×糖尿病史+0.369×心电图-0.007×HGB-0.051×Alb+0.021×Cr,以此建立列线图。模型验证结果显示:Bootstrap内部验证AUC为0.743(95%CI:0.707~0.778),训练集AUC为0.766(95%CI:0.738~0.794),验证集AUC为0.730(95%CI:0.688~0.793)。Hosmer-Lemeshow拟合优度检验结果显示,训练集的P值为0.716,验证集P值为0.408,提示模型拟合良好。训练集和验证集的校准曲线、临床决策曲线及临床影响曲线均表明,该模型具有良好的临床应用价值。 结论 年龄、糖尿病史、心电图、HGB、Alb和Cr是预测PHC患者并发心肌损伤的6个独立影响因素,基于上述指标构建的列线图具有良好的区分度、准确性和临床实用性。 Abstract:Objective To investigate the independent risk factors for concurrent myocardial injury before intervention in patients with primary hepatic carcinoma (PHC), to construct and validate a nomogram prediction model for the early identification of such patients, and to provide a basis for early clinical prevention and management. Methods A retrospective analysis was performed for the clinical data of 1 822 patients with PHC in two medical institutions from January 2019 to June 2025, among whom the 1 518 patients from The Third People’s Hospital of Kunming were used as the training set to construct the nomogram prediction model, and the 304 patients from The Second People’s Hospital of Baoshan were used as the validation set. According to the result of high-sensitivity cardiac troponin T measurement before intervention, the patients with PHC were divided into myocardial injury group and non-myocardial injury group. The univariate analysis, the LASSO regression analysis, and the multivariate Logistic regression analysis were used to identify the risk factors of concurrent myocardial injury in PHC patients before intervention, and then a nomogram prediction model was constructed based on these findings. The independent data of the 304 patients in the validation set were used for external validation, and the area under the receiver operating characteristic curve (AUC), the Hosmer-Lemeshow test, the calibration curve, decision curve analysis, and clinical impact curve were used to assess model performance. Results In the training set, there were 346 patients in the myocardial injury group and 1 172 patients in the non-myocardial injury group, and the prevalence rate of concurrent myocardial injury was 22.79%. The mean age was 56.44±9.45 years, and the male patients accounted for 81.49%. The patients with drinking, smoking, chronic hepatitis B, chronic hepatitis C, hypertension, diabetes, Child-Pugh class A liver disease, BCLC stage B liver disease, or abnormal electrocardiographic findings accounted for 49.34%, 57.44%, 61.73%, 32.48%, 22.66%, 17.19%, 50.53%, 33.86%, and 62.12%, respectively. The univariate analysis, the LASSO regression analysis, and the multivariate Logistic regression analysis showed that age (odds ratio [OR]=1.051, 95% confidence interval [CI]: 1.036 — 1.067, P<0.001), history of diabetes (OR=1.862, 95%CI: 1.346 — 2.574, P<0.001), electrocardiographic findings (OR=1.446, 95%CI: 1.077 — 1.940, P=0.014), hemoglobin (HGB) (OR=0.993, 95%CI: 0.988 — 0.998, P=0.003), albumin (Alb) (OR=0.951, 95%CI: 0.930 — 0.972, P<0.001), and creatinine (Cr) (OR=1.021, 95%CI: 1.016 — 1.026, P<0.001) were independent influencing factors for myocardial injury in PHC patients. A regression equation was established as Logit(Y)=-3.406+0.050×age+0.621×history of diabetes+0.369×electrocardiogram-0.007×HGB-0.051×Alb+0.021×Cr, and a nomogram prediction model was constructed based on these factors. The Bootstrap internal validation of the model yielded an AUC of 0.743 (95%CI: 0.707 — 0.778), and the model had an AUC of 0.766 (95%CI: 0.738 — 0.794) in the training set and 0.730 (95%CI: 0.688 — 0.793) in the validation set. The Hosmer-Lemeshow goodness-of-fit test yielded a P value of 0.716 for the training set and 0.408 for the validation set, suggesting that the model had a good degree of fitting. Calibration curves, decision curve analysis, and clinical impact curves in both the training set and the validation set showed that the model had a good clinical application value. Conclusion Age, history of diabetes, electrocardiographic findings, HGB, Alb, and Cr are independent influencing factors for myocardial injury in patients with PHC, and the nomogram prediction model constructed based on these factors has good discriminatory ability, accuracy, and clinical practicability. -
Key words:
- Liver Neoplasms /
- Myocardial Injury /
- Risk Factors /
- Nomogram
-
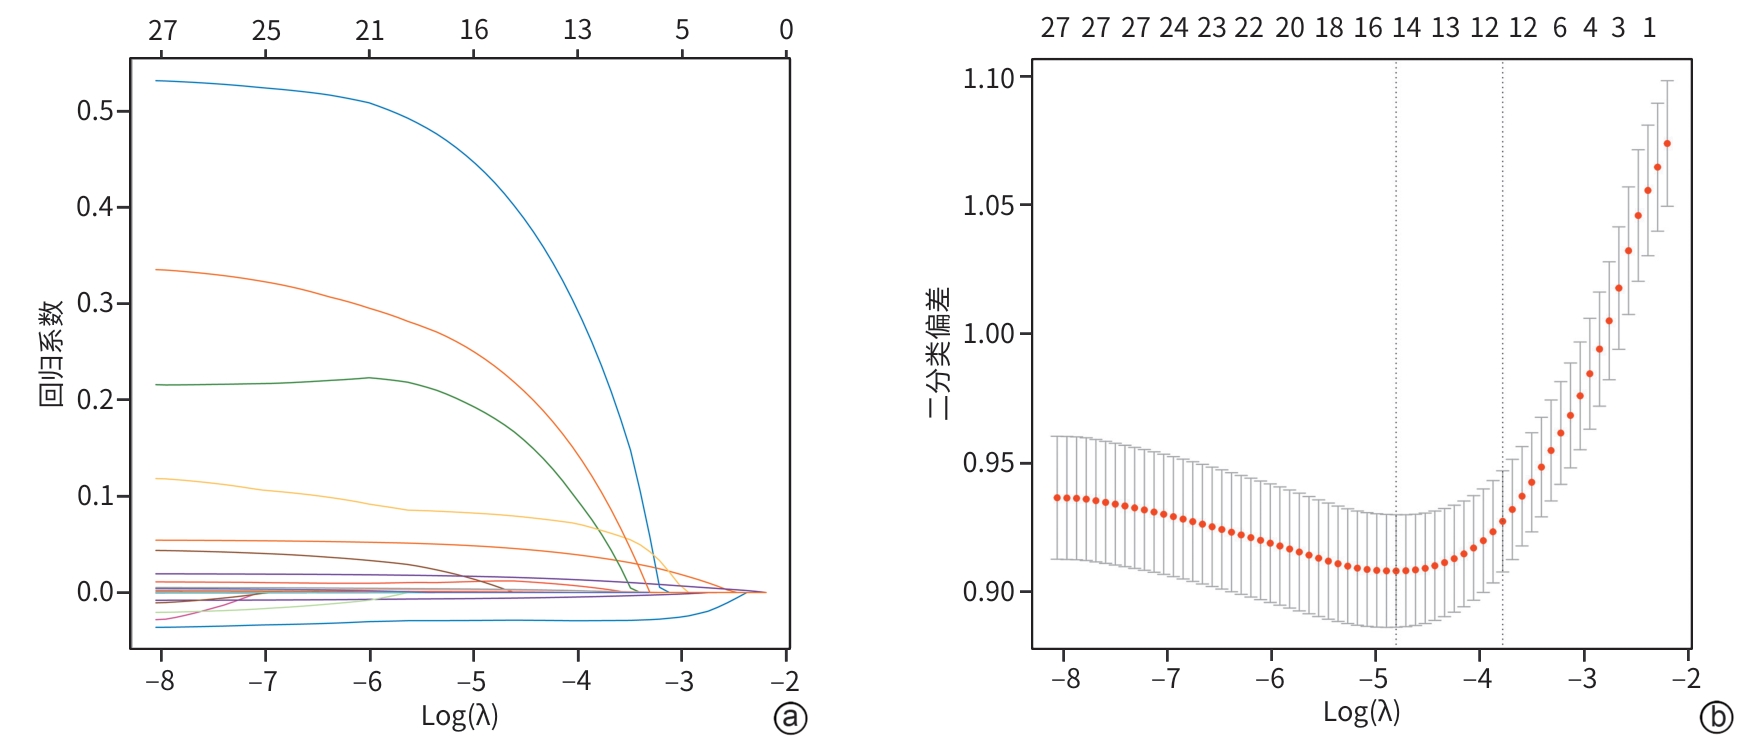
注: a,LASSO回归系数路径图;b,10倍交叉验证曲线。
图 1 基于LASSO回归的变量筛选
Figure 1. Variable selection based on LASSO regression
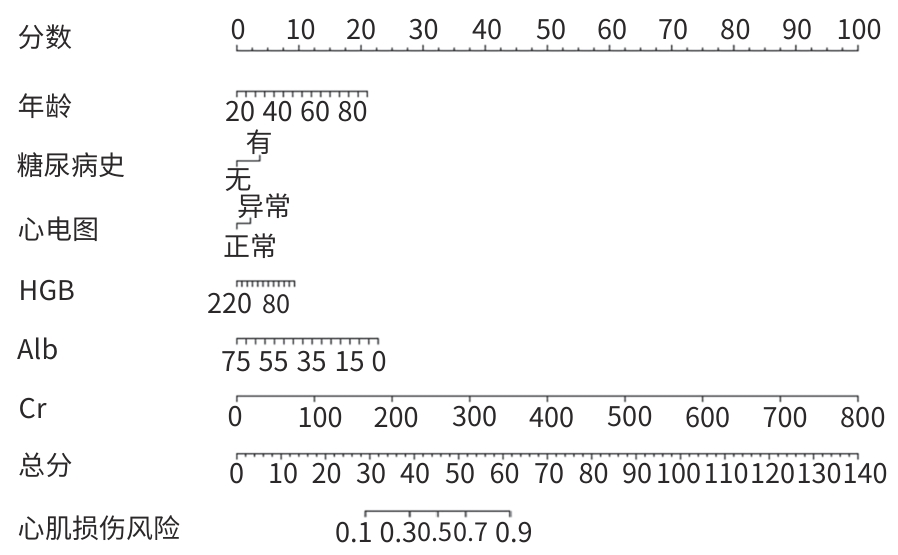
注: HGB,血红蛋白;Alb,白蛋白;Cr,肌酐;PHC,原发性肝癌。
图 2 预测PHC干预前并发心肌损伤风险的列线图
Figure 2. Nomogram for predicting the risk of myocardial injury prior to intervention in patients with PHC
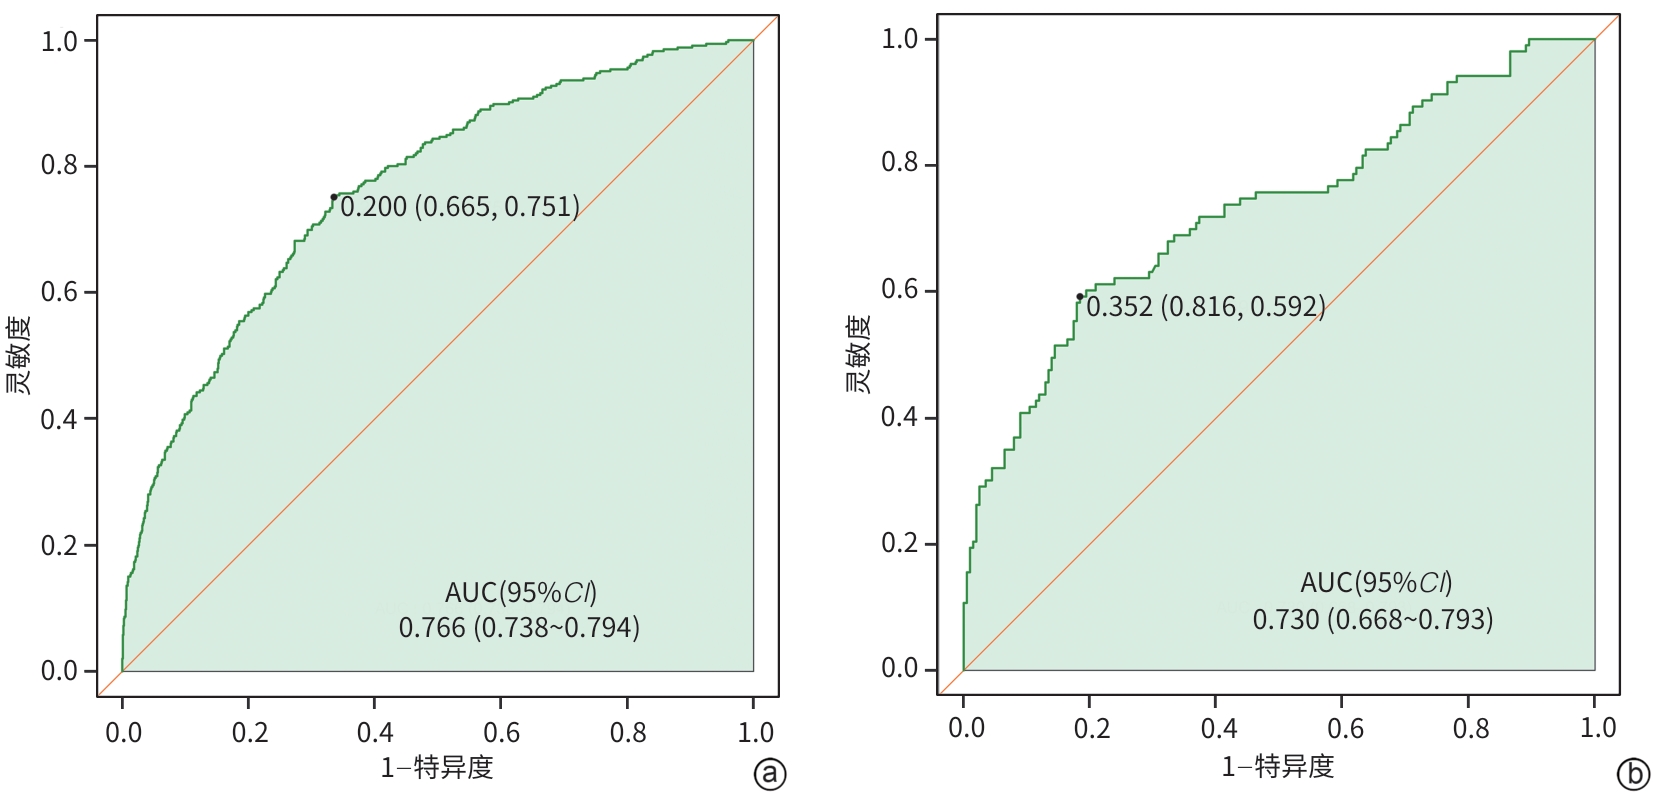
注: a,训练集;b,验证集。PHC,原发性肝癌;ROC曲线,受试者操作特征曲线;AUC,曲线下面积;CI,置信区间。
图 3 训练集与验证集PHC患者并发心肌损伤预测模型的ROC曲线
Figure 3. ROC curves of the prediction model for myocardial injury in PHC patients in the training set and validation set
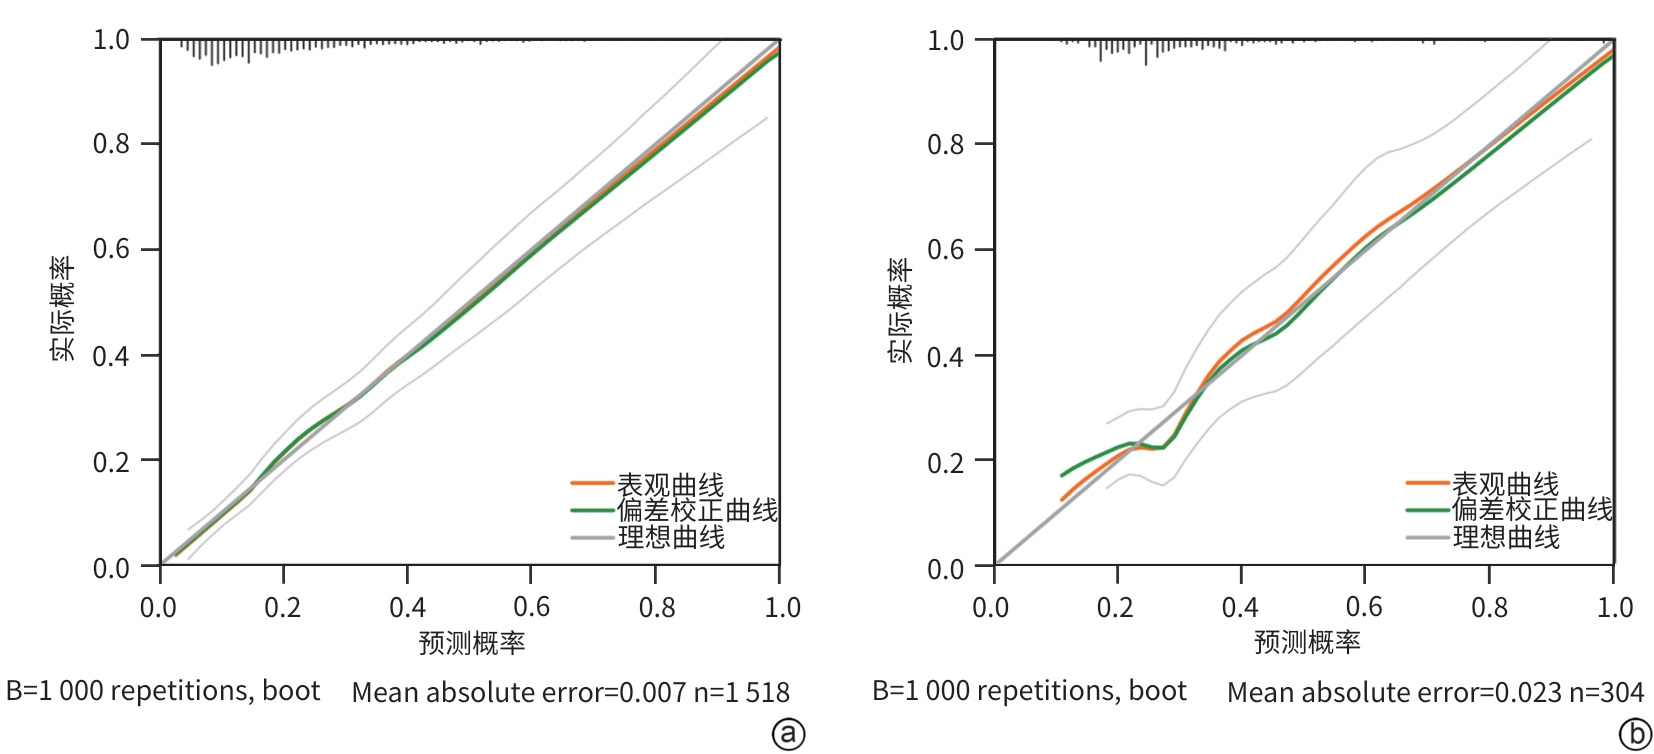
注: a,训练集;b,验证集。PHC,原发性肝癌。
图 4 训练集与验证集PHC患者并发心肌损伤预测模型的校准曲线
Figure 4. Calibration curves of the prediction model for myocardial injury in PHC patients in the training set and validation set
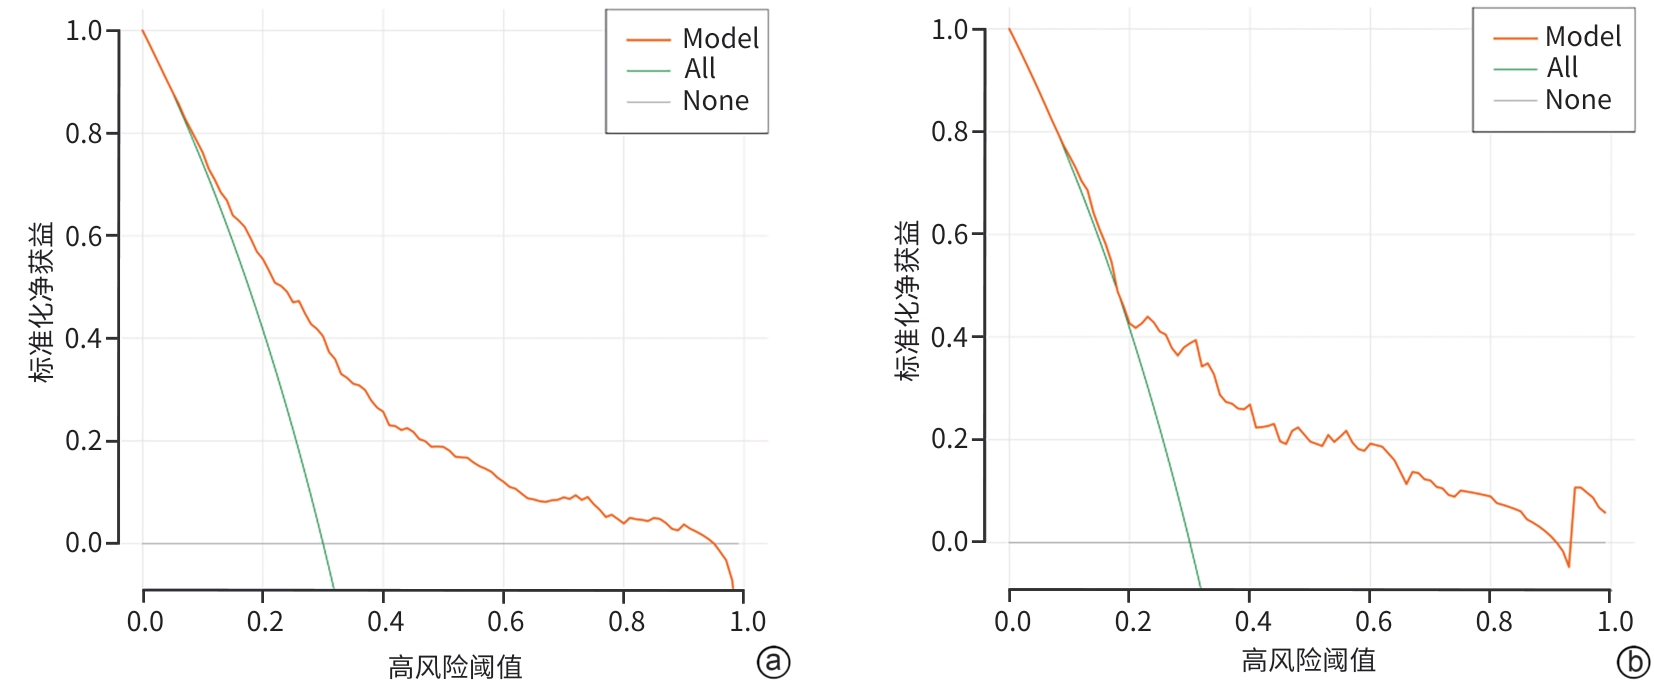
注: a,训练集;b,验证集。PHC,原发性肝癌。
图 5 训练集与验证集PHC患者并发心肌损伤预测模型的临床决策曲线
Figure 5. Clinical decision curve analysis of the prediction model for myocardial injury in patients with PHC in the training set and validation set
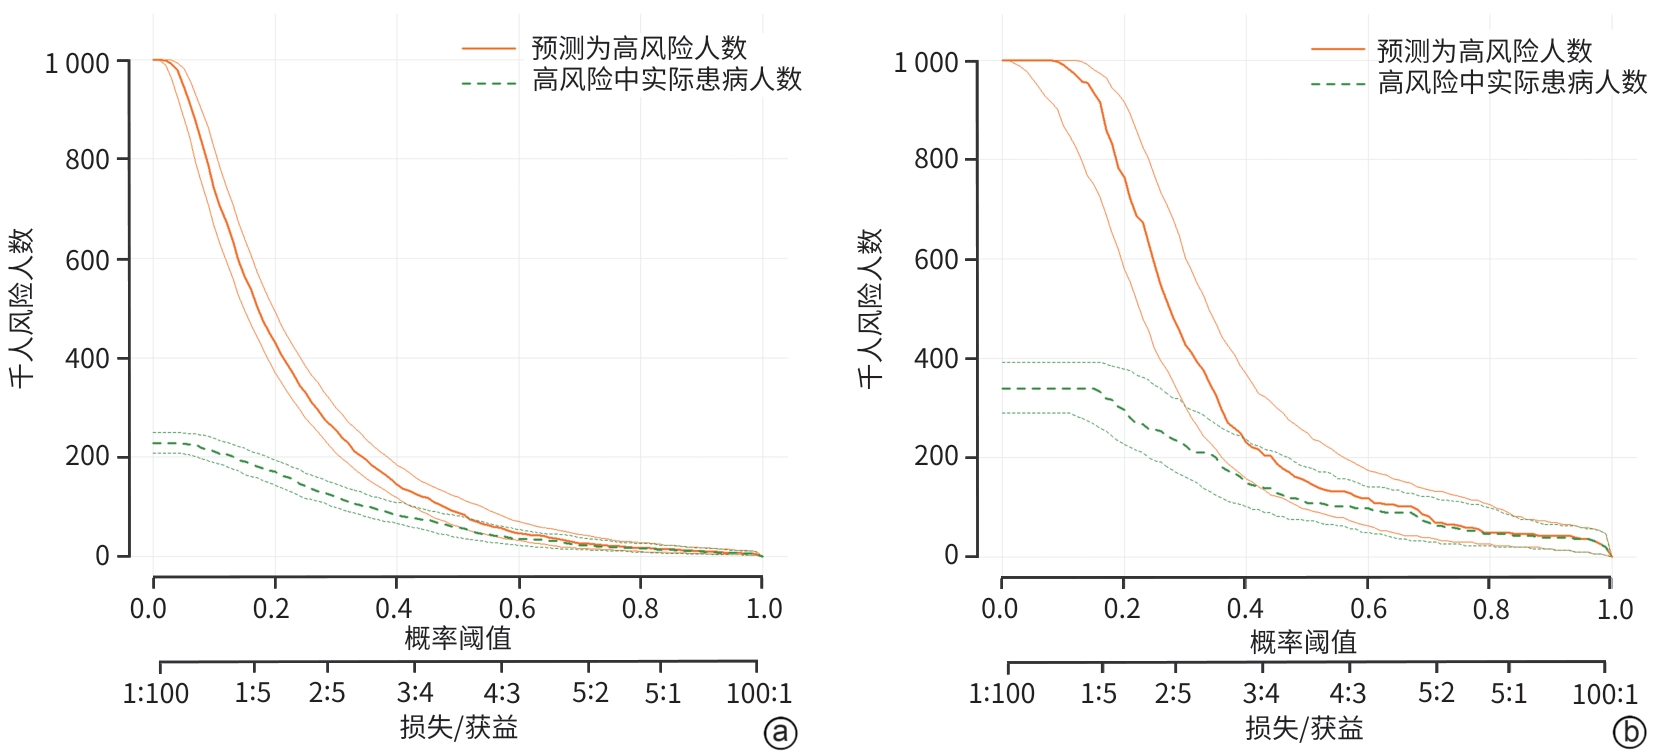
注: a,训练集;b,验证集。PHC,原发性肝癌。
图 6 训练集与验证集PHC患者并发心肌损伤预测模型的临床影响曲线
Figure 6. Clinical impact curve of the prediction model for myocardial injury in patients with PHC in the training set and validation set
表 1 训练集心肌损伤组与非心肌损伤组基线资料比较
Table 1. Comparison of baseline characteristics between the myocardial injury group and the non-myocardial injury group in training set
项目 非心肌损伤组(n=1 172) 心肌损伤组(n=346) 统计值 P值 年龄(岁) 55.44±9.15 59.82±9.69 t=-7.730 <0.001 性别[例(%)] χ2=0.094 0.759 男 957(81.66) 280(80.92) 女 215(18.34) 66(19.08) 饮酒史[例(%)] χ2=0.794 0.373 无 601(51.28) 168(48.55) 有 571(48.72) 178(51.45) 吸烟史[例(%)] χ2=0.047 0.828 无 497(42.41) 149(43.06) 有 675(57.59) 197(56.94) CHB[例(%)] χ2=2.919 0.088 无 435(37.12) 146(42.20) 有 737(62.88) 200(57.80) CHC[例(%)] χ2=2.207 0.137 无 780(66.55) 245(70.81) 有 392(33.45) 101(29.19) 高血压史[例(%)] χ2=12.917 <0.001 无 931(79.44) 243(70.23) 有 241(20.56) 103(29.77) 糖尿病史[例(%)] χ2=15.795 <0.001 无 995(84.90) 262(75.72) 有 177(15.10) 84(24.28) Child-Pugh分级[例(%)] χ2=56.310 <0.001 A级 651(55.55) 116(33.53) B级 357(30.46) 141(40.75) C级 164(13.99) 89(25.72) BCLC分期[例(%)] χ2=48.945 <0.001 0期 215(18.34) 33(9.54) A期 194(16.55) 31(8.96) B期 396(33.79) 118(34.10) C期 202(17.24) 73(21.10) D期 165(14.08) 91(26.30) 心电图[例(%)] χ2=24.272 <0.001 正常 483(41.21) 92(26.59) 异常 689(58.79) 254(73.41) 注:CHB,慢性乙型肝炎;CHC,慢性丙型肝炎;Child-Pugh分级,蔡尔德-皮尤分级;BCLC分期,巴塞罗那肝癌临床分期。
 下载: 导出CSV
表 2 训练集心肌损伤组与非心肌损伤组实验室指标比较
Table 2. Comparison of laboratory parameters between the myocardial injury group and the non-myocardial injury group
项目 非心肌损伤组(n=1 172) 心肌损伤组(n=346) 统计值 P值 WBC(×109/L) 4.41(3.32~6.08) 5.07(3.70~7.20) Z=-4.405 <0.001 NEUT(×109/L) 2.34(1.54~3.64) 2.88(1.59~4.92) Z=-3.925 <0.001 LYM(×109/L) 1.17(0.77~1.72) 0.98(0.64~1.59) Z=-3.240 0.001 HGB(g/L) 132.05±32.39 116.58±33.22 t=7.760 <0.001 PLT(×109/L) 108.00(72.00~163.00) 107.00(70.75~182.25) Z=-0.821 0.412 PCT(ng/mL) 0.10(0.05~0.26) 0.21(0.09~0.66) Z=-8.140 <0.001 hs-CRP(mg/mL) 4.56(1.14~17.69) 11.32(2.84~36.42) Z=-6.892 <0.001 PT(s) 15.10(14.10~16.50) 15.90(14.40~18.00) Z=-4.971 <0.001 FIB(g/L) 2.67(2.11~3.42) 2.61(1.87~3.55) Z=-0.782 0.434 AFP(ng/mL) 16.24(3.97~665.97) 36.68(4.14~2 050.25) Z=-2.351 0.019 CEA(ng/mL) 2.98(1.96~4.55) 3.56(2.35~5.08) Z=-4.069 <0.001 TBil(μmol/L) 22.40(14.90~38.98) 27.90(16.78~59.40) Z=-4.400 <0.001 AST(U/L) 45.00(31.00~82.00) 58.50(36.00~115.00) Z=-4.616 <0.001 ALT(U/L) 34.00(22.00~54.00) 37.00(21.00~64.00) Z=-1.937 0.053 Alb(g/L) 35.00(29.40~40.10) 30.30(25.50~35.60) Z=-9.003 <0.001 GGT(U/L) 84.00(42.00~186.00) 114.25(57.75~232.50) Z=-4.192 <0.001 ALP(U/L) 140.50(101.00~207.00) 162.00(116.75~251.25) Z=-4.835 <0.001 ChE(U/L) 4 352.50(2 825.00~6 313.75) 3 133.50(1 923.00~4 836.50) Z=-7.350 <0.001 TBA(μmol/L) 15.60(5.50~42.25) 23.25(7.58~63.83) Z=-3.841 <0.001 TG(mmol/L) 0.89(0.66~1.29) 0.93(0.66~1.32) Z=-0.338 0.735 TC(mmol/L) 3.73(3.10~4.42) 3.49(2.79~4.40) Z=-2.978 0.003 LDL(mmol/L) 2.26(1.75~2.89) 2.15(1.52~2.94) Z=-1.625 0.104 Cr(μmol/L) 60.00(49.00~72.00) 71.00(56.00~95.00) Z=-8.581 <0.001 BA(μmol/L) 31.85(21.00~45.13) 36.60(22.75~53.40) Z=-3.740 <0.001 CD4+(个/μL) 397.17(269.58~583.03) 367.96(245.93~544.07) Z=-2.246 0.025 CD8+(个/μL) 242.58(139.59~395.35) 222.04(122.34~362.47) Z=-2.014 0.044 CD4+/CD8+ 1.69(1.16~2.33) 1.74(1.21~2.50) Z=-1.304 0.192 IL-6(pg/mL) 11.93(4.91~29.80) 22.66(7.90~62.27) Z=-6.524 <0.001 TNF-α(pg/mL) 2.45(1.48~5.87) 2.96(1.71~7.42) Z=-2.371 0.018 注:WBC,白细胞计数;NEUT,中性粒细胞计数;LYM,淋巴细胞计数;PLT,血小板;HGB,血红蛋白;PCT,降钙素原;hs-CRP,超敏C反应蛋白;PT,凝血酶原时间;FIB,纤维蛋白原;AFP,甲胎蛋白;CEA,癌胚抗原;TBil,总胆红素;AST,天冬氨酸氨基转移酶;ALT,丙氨酸氨基转移酶;Alb,白蛋白;GGT,γ-谷氨酰转移酶;ALP,碱性磷酸酶;ChE,胆碱酯酶;TBA,总胆汁酸;TG,甘油三酯;TC,总胆固醇;LDL,低密度脂蛋白;Cr,肌酐;BA,血氨;CD4+,CD4 T细胞计数;CD8+,CD8 T细胞计数;IL-6,白细胞介素6;TNF-α,肿瘤坏死因子α。
下载: 导出CSV
表 3 PHC患者并发心肌损伤的多因素Logistic回归分析
Table 3. Multivariate Logistic regression analysis of myocardial injury in patients with PHC
参数 β值 SE Wald χ2 P值 OR(95%CI) 年龄 0.050 0.007 46.500 <0.001 1.051(1.036~1.067) 糖尿病史 0.621 0.165 14.134 <0.001 1.862(1.346~2.574) 心电图 0.369 0.150 6.036 0.014 1.446(1.077~1.940) HGB -0.007 0.002 8.897 0.003 0.993(0.988~0.998) Alb -0.051 0.011 20.400 <0.001 0.951(0.930~0.972) Cr 0.021 0.003 63.270 <0.001 1.021(1.016~1.026) 注:PHC,原发性肝癌;HGB,血红蛋白;Alb,白蛋白;Cr,肌酐;OR,比值比;CI,置信区间;SE,标准误。
下载: 导出CSV
-
[1] Rumgay H, Arnold M, Ferlay J, et al. Global burden of primary liver cancer in 2020 and predictions to 2040[J]. J Hepatol, 2022, 77( 6): 1598- 1606. DOI: 10.1016/j.jhep.2022.08.021. [2] Berkemeyer S. Primary liver cancers: Connecting the dots of cellular studies and epidemiology with metabolomics[J]. Int J Mol Sci, 2023, 24( 3): 2409. DOI: 10.3390/ijms24032409. [3] Han B F, Zheng R S, Zeng H M, et al. Cancer incidence and mortality in China, 2022[J]. J Natl Cancer Cent, 2024, 4( 1): 47- 53. DOI: 10.1016/j.jncc.2024.01.006. [4] Cao Guangwen. Epidemiological characteristics and precise prophylaxis and control of primary liver cancer in China[J]. J Guangxi Med Univ, 2024, 41( 11): 1455- 1463. DOI: 10.16190/j.cnki.45-1211/r.2024.11.002.曹广文. 我国原发性肝癌的流行病学特征及精准防控[J]. 广西医科大学学报, 2024, 41( 11): 1455- 1463. DOI: 10.16190/j.cnki.45-1211/r.2024.11.002. [5] Liu B H, Li Q, Ding H G, et al. Myocardial injury is a risk factor for 6-week mortality in liver cirrhosis associated esophagogastric variceal bleeding[J]. Sci Rep, 2023, 13( 1): 6237. DOI: 10.1038/s41598-023-33325-6. [6] Abdullah T, Şentürk M, Gökduman H C, et al. Perioperative myocardial injury and acute kidney injury in patients undergoing hepatic resection: Incidence, risk factors, and effects on outcomes[J]. J Clin Med, 2025, 14( 17): 6080. DOI: 10.3390/jcm14176080. [7] Cao L Z, Wang X Y, Yan Y Z, et al. Analysis of competing risks of cardiovascular death in patients with hepatocellular carcinoma: A population-based study[J]. Medicine, 2023, 102( 51): e36705. DOI: 10.1097/MD.0000000000036705. [8] National Health Commission of the People’s Republic of China. Standard for diagnosis and treatment of primary liver cancer(2024 edition)[J]. J Clin Hepatol, 2024, 40( 5): 893- 918. DOI: 10.12449/JCH240508.中华人民共和国国家卫生健康委员会. 原发性肝癌诊疗指南(2024年版)[J]. 临床肝胆病杂志, 2024, 40( 5): 893- 918. DOI: 10.12449/JCH240508. [9] Thygesen K, Alpert J S, Jaffe A S, et al. Fourth universal definition of myocardial infarction(2018)[J]. J Am Coll Cardiol, 2018, 72( 18): 2231- 2264. DOI: 10.1016/j.jacc.2018.08.1038. [10] Lou Yan, Ai Yingchun, Shan Xin. Changes and clinical significance of myocardial injury markers in patients with liver cirrhosis[J]. Stud Trace Elem Heal, 2020, 37( 4): 13- 14.娄妍, 艾迎春, 单昕. 肝硬化患者心肌损伤标志物水平变化及临床意义[J]. 微量元素与健康研究, 2020, 37( 4): 13- 14. [11] Huang Wan. Huangwan clinical electrocardiogram[M]. Beijing: People’s Medical Publishing House, 2009.黄宛. 黄宛临床心电图学[M]. 北京: 人民卫生出版社, 2009. [12] Chinese Society of Electrocardiology, Chinese Society of Cardiac Pacing and Electrophysiology, compiled. Recommendations for the standardization and interpretation of the electrocardiogram and its clinical application international guidelines 2009[M]. Beijing: China Environmental Science Press, 2009.中国心电学会, 中国心律学会 编译. 心电图标准化和解析的建议与临床应用国际指南2009[M]. 北京: 中国环境科学出版社, 2009. [13] The Noninvasive Cardiac Testing Group of the Military Cardiovascular Professional Committee, Task Force on“Chinese Expert Consensus Statement on the Standardization of Electrocardiography Diagnostic Terminology 2019”. Chinese expert consensus statement on the standardization of electrocardiography diagnostic terminology 2019[J]. J Pract Electrocardiol, 2019, 28( 3): 161- 165. DOI: 10.13308/j.issn.2095-9354.2019.03.002.全军心血管专业委员会心脏无创检测学组,《心电图诊断术语规范化中国专家共识(2019)》编写专家组. 心电图诊断术语规范化中国专家共识(2019)[J]. 实用心电学杂志, 2019, 28( 3): 161- 165. DOI: 10.13308/j.issn.2095-9354.2019.03.002. [14] Galun D, Mijac D, Filipovic A, et al. Precision medicine for hepatocellular carcinoma: Clinical perspective[J]. J Pers Med, 2022, 12( 2): 149. DOI: 10.3390/jpm12020149. [15] Seehofer D, Sucher R, Denecke T. Resektion und transplantation bei hepatozellulärem karzinom und intrahepatischem cholangiokarzinom[J]. Der Radiologe, 2022, 62( 3): 210- 218. DOI: 10.1007/s00117-021-00962-9. [16] Wurigumenle, Qiqige. Progress in the study of risk factors associated with primary liver cancer[J]. Adv Clin Med, 2024, 14( 2): 4479- 4485. DOI: 10.12677/ACM.2024.142622.乌日古门勒, 其其格. 肝癌相关危险因素的研究进展[J]. 临床医学进展, 2024, 14( 2): 4479- 4485. DOI: 10.12677/ACM.2024.142622. [17] Rosenthal B E, Hoteit M A, Lluri G, et al. Characteristics and survival outcomes of hepatocellular carcinoma after the fontan operation[J]. JACC Adv, 2025, 4( 4): 101646. DOI: 10.1016/j.jacadv.2025.101646. [18] Karim H, Rahman A, Fatin M. The impact of cardiovascular complications on mortality and public health in patients with hepatocellular carcinoma: A multicenter cohort study[J]. Clin Epidemiol Public Health, 2025, 3( 1): 1- 9. DOI: 10.25163/health.3110225. [19] Wang L D, Wang T, Zhang W, et al. Survival and cardiovascular disease mortality among primary liver cancer patients: A population-based study[J]. Heliyon, 2024, 10( 19): e37869. DOI: 10.1016/j.heliyon.2024.e37869. [20] Xu H W, Zhang Y, Gao Y J. Prevalence and risk factors for cirrhotic cardiomyopathy: A prospective cross-sectional study[J]. Eur J Gastroenterol Hepatol, 2024, 36( 4): 469- 475. DOI: 10.1097/MEG.0000000000002716. [21] Xanthopoulos A, Starling R C, Kitai T, et al. Heart failure and liver disease cardiohepatic interactions[J]. JACC Heart Fail, 2019, 7( 2): 87- 97. DOI: 10.1016/j.jchf.2018.10.007. [22] Liu H Q, Nguyen H H, Hwang S Y, et al. Oxidative mechanisms and cardiovascular abnormalities of cirrhosis and portal hypertension[J]. Int J Mol Sci, 2023, 24( 23): 16805. DOI: 10.3390/ijms242316805. [23] Zhang Yonghua, Kuang Gang, Zhao Jianmin. Clinical abnormal manifestations and discussion of myocardial zymogram in tumor myocardial infarction and other diseases[J]. Med Forum, 2025, 29( 14): 31- 33, 56. DOI: 10.19435/j.1672-1721.2025.14.009.张勇华, 匡刚, 赵剑敏. 肿瘤 心肌梗死等疾病中心肌酶谱的临床异常表现及探讨[J]. 基层医学论坛, 2025, 29( 14): 31- 33, 56. DOI: 10.19435/j.1672-1721.2025.14.009. [24] Zeng Hongmei, Cao Maomao, Zheng Rongshou, et al. Trend analysis of age of diagnosis for liver cancer in cancer registry areas of China, 2000-2014[J]. Chin J Prev Med, 2018, 52( 6): 573- 578. DOI: 10.3760/cma.j.issn.0253-9624.2018.06.004.曾红梅, 曹毛毛, 郑荣寿, 等. 2000—2014年中国肿瘤登记地区肝癌发病年龄变化趋势分析[J]. 中华预防医学杂志, 2018, 52( 6): 573- 578. DOI: 10.3760/cma.j.issn.0253-9624.2018.06.004. [25] An Lan, Zeng Hongmei, Zheng Rongshou, et al. Liver cancer epidemiology in China, 2015[J]. Chin J Oncol, 2019, 41( 10): 721- 727. DOI: 10.3760/cma.j.issn.0253-3766.2019.10.001.安澜, 曾红梅, 郑荣寿, 等. 2015年中国肝癌流行情况分析[J]. 中华肿瘤杂志, 2019, 41( 10): 721- 727. DOI: 10.3760/cma.j.issn.0253-3766.2019.10.001. [26] Li Jiaxin, Qian Xin, Zhao Junjie, et al. Effect of aging on cardiac structure and function and its mechanism[J]. Chin Heart J, 2020, 32( 2): 190- 192, 205. DOI: 10.12125/j.chj.201905028.李嘉欣, 钱欣, 赵俊捷, 等. 衰老对心脏结构和功能的影响与机制的研究[J]. 心脏杂志, 2020, 32( 2): 190- 192, 205. DOI: 10.12125/j.chj.201905028. [27] Wang Xusheng, Li Siting, Fang Zhong. The relationship between heart rate variability, QRS wave width, QT dispersion and adverse cardiovascular events in elderly patients with acute myocardial infarction[J]. Clin J Med Offic, 2024, 52( 9): 914- 916. DOI: 10.16680/j.1671-3826.2024.09.08.王旭升, 栗思婷, 方中. 老年急性心肌梗死患者心率变异性、QRS波宽度、QT离散度与不良心血管事件发生关系[J]. 临床军医杂志, 2024, 52( 9): 914- 916. DOI: 10.16680/j.1671-3826.2024.09.08. [28] Ritchie R H, Abel E D. Basic mechanisms of diabetic heart disease[J]. Circ Res, 2020, 126( 11): 1501- 1525. DOI: 10.1161/CIRCRESAHA.120.315913. [29] Pang Yanqiu, Wan Na, Guo Rui, et al. Application of cardiac magnetic resonance tissue tracking and T1 mapping technology in the assessment of diabetic myocardial injury[J]. Chin J Magn Reson Imaging, 2025, 16( 9): 82- 89. DOI: 10.12015/issn.1674-8034.2025.09.013.庞艳秋, 万娜, 郭瑞, 等. 心脏磁共振组织追踪及T1 mapping技术对糖尿病心肌损伤评估的应用研究[J]. 磁共振成像, 2025, 16( 9): 82- 89. DOI: 10.12015/issn.1674-8034.2025.09.013. [30] Cai X Y, Zhang Y L, Li M J, et al. Association between prediabetes and risk of all cause mortality and cardiovascular disease: Updated meta-analysis[J]. BMJ, 2020, 370: m2297. DOI: 10.1136/bmj.m2297. [31] Wong N D, Sattar N. Cardiovascular risk in diabetes mellitus: Epidemiology, assessment and prevention[J]. Nat Rev Cardiol, 2023, 20( 10): 685- 695. DOI: 10.1038/s41569-023-00877-z. [32] Nakamura K, Miyoshi T, Yoshida M, et al. Pathophysiology and treatment of diabetic cardiomyopathy and heart failure in patients with diabetes mellitus[J]. Int J Mol Sci, 2022, 23( 7): 3587. DOI: 10.3390/ijms23073587. [33] Xiong Yuqi, Li Xuejun. Common risk factors of cardiovascular diseases and malignant tumors and the effect of drugs[J]. Acta Pharm Sin, 2020, 55( 1): 1- 7. DOI: 10.16438/j.0513-4870.2019-0756.熊宇麒, 李学军. 心血管疾病与恶性肿瘤的共同危险因素及药物的影响[J]. 药学学报, 2020, 55( 1): 1- 7. DOI: 10.16438/j.0513-4870.2019-0756. [34] D’Imperio S, Monasky M M, Micaglio E, et al. Brugada syndrome: Warning of a systemic condition?[J]. Front Cardiovasc Med, 2021, 8: 771349. DOI: 10.3389/fcvm.2021.771349. [35] Zhi L, Chen Z H, Deng J. Parameter changes and influencing factors in sixty patients with interventional surgery for liver cancer diagnoses[J]. World J Gastrointest Surg, 2025, 17( 2): 99581. DOI: 10.4240/wjgs.v17.i2.99581. [36] Ding Tianjia, Sun Tao, Wu Mingfeng, et al. Risk factors of electrocardiogram abnormalities in patients with primary liver cancer and its value in predicting prognosis[J]. J Clin Med Pract, 2024, 28( 3): 100- 104. DOI: 10.7619/jcmp.20233012.丁天嘉, 孙涛, 吴名凤, 等. 原发性肝癌患者心电图异常的危险因素及其预测预后的价值[J]. 实用临床医药杂志, 2024, 28( 3): 100- 104. DOI: 10.7619/jcmp.20233012. [37] Kyriakou M, Kadoglou N P E, Sokratous S, et al. The relationship between electrocardiographic findings and cardiac magnetic resonance results in patients with acute myocarditis: A retrospective analysis[J]. Medicina, 2025, 61( 8): 1444. DOI: 10.3390/medicina61081444. [38] Meischl T, Balcar L, Park Y R, et al. Anaemia is independently associated with mortality in patients with hepatocellular carcinoma[J]. ESMO Open, 2024, 9( 6): 103593. DOI: 10.1016/j.esmoop.2024.103593. [39] Asif A, Wei J, Lauzon M, et al. Anemia and long-term cardiovascular outcomes in women with suspected ischemia- The Women’s Ischemia Syndrome Evaluation(WISE)[J]. Am Heart J Plus, 2021, 10: 100059. DOI: 10.1016/j.ahjo.2021.100059. [40] Qiu Yue, Sun Ding, Lu Yan. Predictive value of nutritional risk index for postoperative complications in elderly patients with liver cancer[J]. Chin J Gerontol, 2022, 42( 20): 4958- 4961. DOI: 10.3969/j.issn.1005-9202.2022.20.018.邱玥, 孙鼎, 陆艳. 老年营养风险指数对老年肝癌患者术后并发症的预测价值[J]. 中国老年学杂志, 2022, 42( 20): 4958- 4961. DOI: 10.3969/j.issn.1005-9202.2022.20.018. [41] Wada H, Dohi T, Miyauchi K, et al. Long-term clinical impact of serum albumin in coronary artery disease patients with preserved renal function[J]. Nutr Metab Cardiovasc Dis, 2018, 28( 3): 285- 290. DOI: 10.1016/j.numecd.2017.11.005. [42] Yoshioka G, Tanaka A, Nishihira K, et al. Prognostic impact of serum albumin for developing heart failure remotely after acute myocardial infarction[J]. Nutrients, 2020, 12( 9): 2637. DOI: 10.3390/nu12092637. [43] Suzuki S, Hashizume N, Kanzaki Y, et al. Prognostic significance of serum albumin in patients with stable coronary artery disease treated by percutaneous coronary intervention[J]. PLoS One, 2019, 14( 7): e0219044. DOI: 10.1371/journal.pone.0219044. [44] Prastaro M, Nardi E, Paolillo S, et al. Cardiorenal syndrome: Pathophysiology as a key to the therapeutic approach in an under-diagnosed disease[J]. J Clin Ultrasound, 2022, 50( 8): 1110- 1124. DOI: 10.1002/jcu.23265. [45] de Rosa S, Greco M, Rauseo M, et al. The good, the bad, and the serum creatinine: Exploring the effect of muscle mass and nutrition[J]. Blood Purif, 2023, 52( 9-10): 775- 785. DOI: 10.1159/000533173. [46] Vasquez F, Tiscornia C, Lorca-Ponce E, et al. Cardiorenal syndrome: Molecular pathways linking cardiovascular dysfunction and chronic kidney disease progression[J]. Int J Mol Sci, 2025, 26( 15): 7440. DOI: 10.3390/ijms26157440. [47] Marx-Schütt K, Cherney D Z I, Jankowski J, et al. Cardiovascular disease in chronic kidney disease[J]. Eur Heart J, 2025, 46( 23): 2148- 2160. DOI: 10.1093/eurheartj/ehaf167. [48] Jankowski J, Floege J, Fliser D, et al. Cardiovascular disease in chronic kidney disease: Pathophysiological insights and therapeutic options[J]. Circulation, 2021, 143( 11): 1157- 1172. DOI: 10.1161/CIRCULATIONAHA.120.050686. [49] Clementi A, Virzì G M, Sorbello M, et al. Hepato-renal crosstalk in acute and chronic disease: From shared pathways to therapeutic targets[J]. Biomedicines, 2025, 13( 7): 1618. DOI: 10.3390/biomedicines13071618. [50] Zhu J J, Liu W X, Li J, et al. A small increase in serum creatinine within 48 h of hospital admission is an independent predictor of in-hospital adverse outcomes in patients with ST-segment elevation myocardial infarction undergoing primary percutaneous coronary intervention: Findings from the improving care for cardiovascular disease in the China Project[J]. Cardiol Res Pract, 2023, 2023: 1374206. DOI: 10.1155/2023/1374206. -

 本文二维码
计量
- 文章访问数: 15
- HTML全文浏览量: 8
- PDF下载量: 0
- 被引次数: 0


