

 PDF下载 ( 1220 KB)

重症肝病出凝血再平衡的机制与临床管理策略
DOI: 10.12449/JCH260904
Mechanism and clinical management strategies of rebalanced hemostasis in severe liver disease
-
摘要: 重症肝病常伴凝血酶原时间或国际标准化比值延长、血小板减少和纤维蛋白原异常,传统上易被视为低凝和出血倾向状态。近年研究表明,肝病相关出凝血异常并非单纯促凝因子缺乏,而是在促凝因子与天然抗凝因子同步下降、血小板和纤溶系统异常、血管性血友病因子/血管性血友病因子裂解蛋白酶轴失衡及内皮激活等多重机制作用下形成的脆弱再平衡。本文综述重症肝病出凝血再平衡的关键机制、常规凝血指标局限、不同疾病状态下的凝血特征及临床管理转化。临床决策应从“纠正化验值”转向“识别炎症-内皮-凝血-纤溶网络失稳”,按疾病阶段和出血/血栓风险进行个体化评估。Abstract: Severe liver disease is frequently accompanied by prolonged prothrombin time or international normalized ratio, thrombocytopenia, and abnormal fibrinogen level, which have traditionally been interpreted as hypocoagulability and a bleeding tendency. Recent studies have shown that hemostatic abnormalities in liver disease do not simply result from deficiency of procoagulant factors, but represent a fragile rebalanced hemostatic state shaped by multiple mechanisms including parallel reductions in procoagulant factors and natural anticoagulants, platelet and fibrinolytic abnormalities, imbalance of the von Willebrand factor/a disintegrin and metalloproteinase with a thrombospondin type 1 motif member 13 axis, and endothelial activation. This article reviews the key mechanisms of rebalanced hemostasis in severe liver disease, the limitations of conventional coagulation markers, coagulation features across different disease states, and their implications for clinical management. Clinical decision-making should shift from correcting abnormal laboratory values to identifying destabilization of the inflammation-endothelium-coagulation-fibrinolysis network, with individualized assessment based on disease stage and the risk of bleeding/thrombosis.
-
Key words:
- Liver Failure /
- Liver Cirrhosis /
- Blood Coagulation Disorders /
- Rebalanced Hemostasis
-
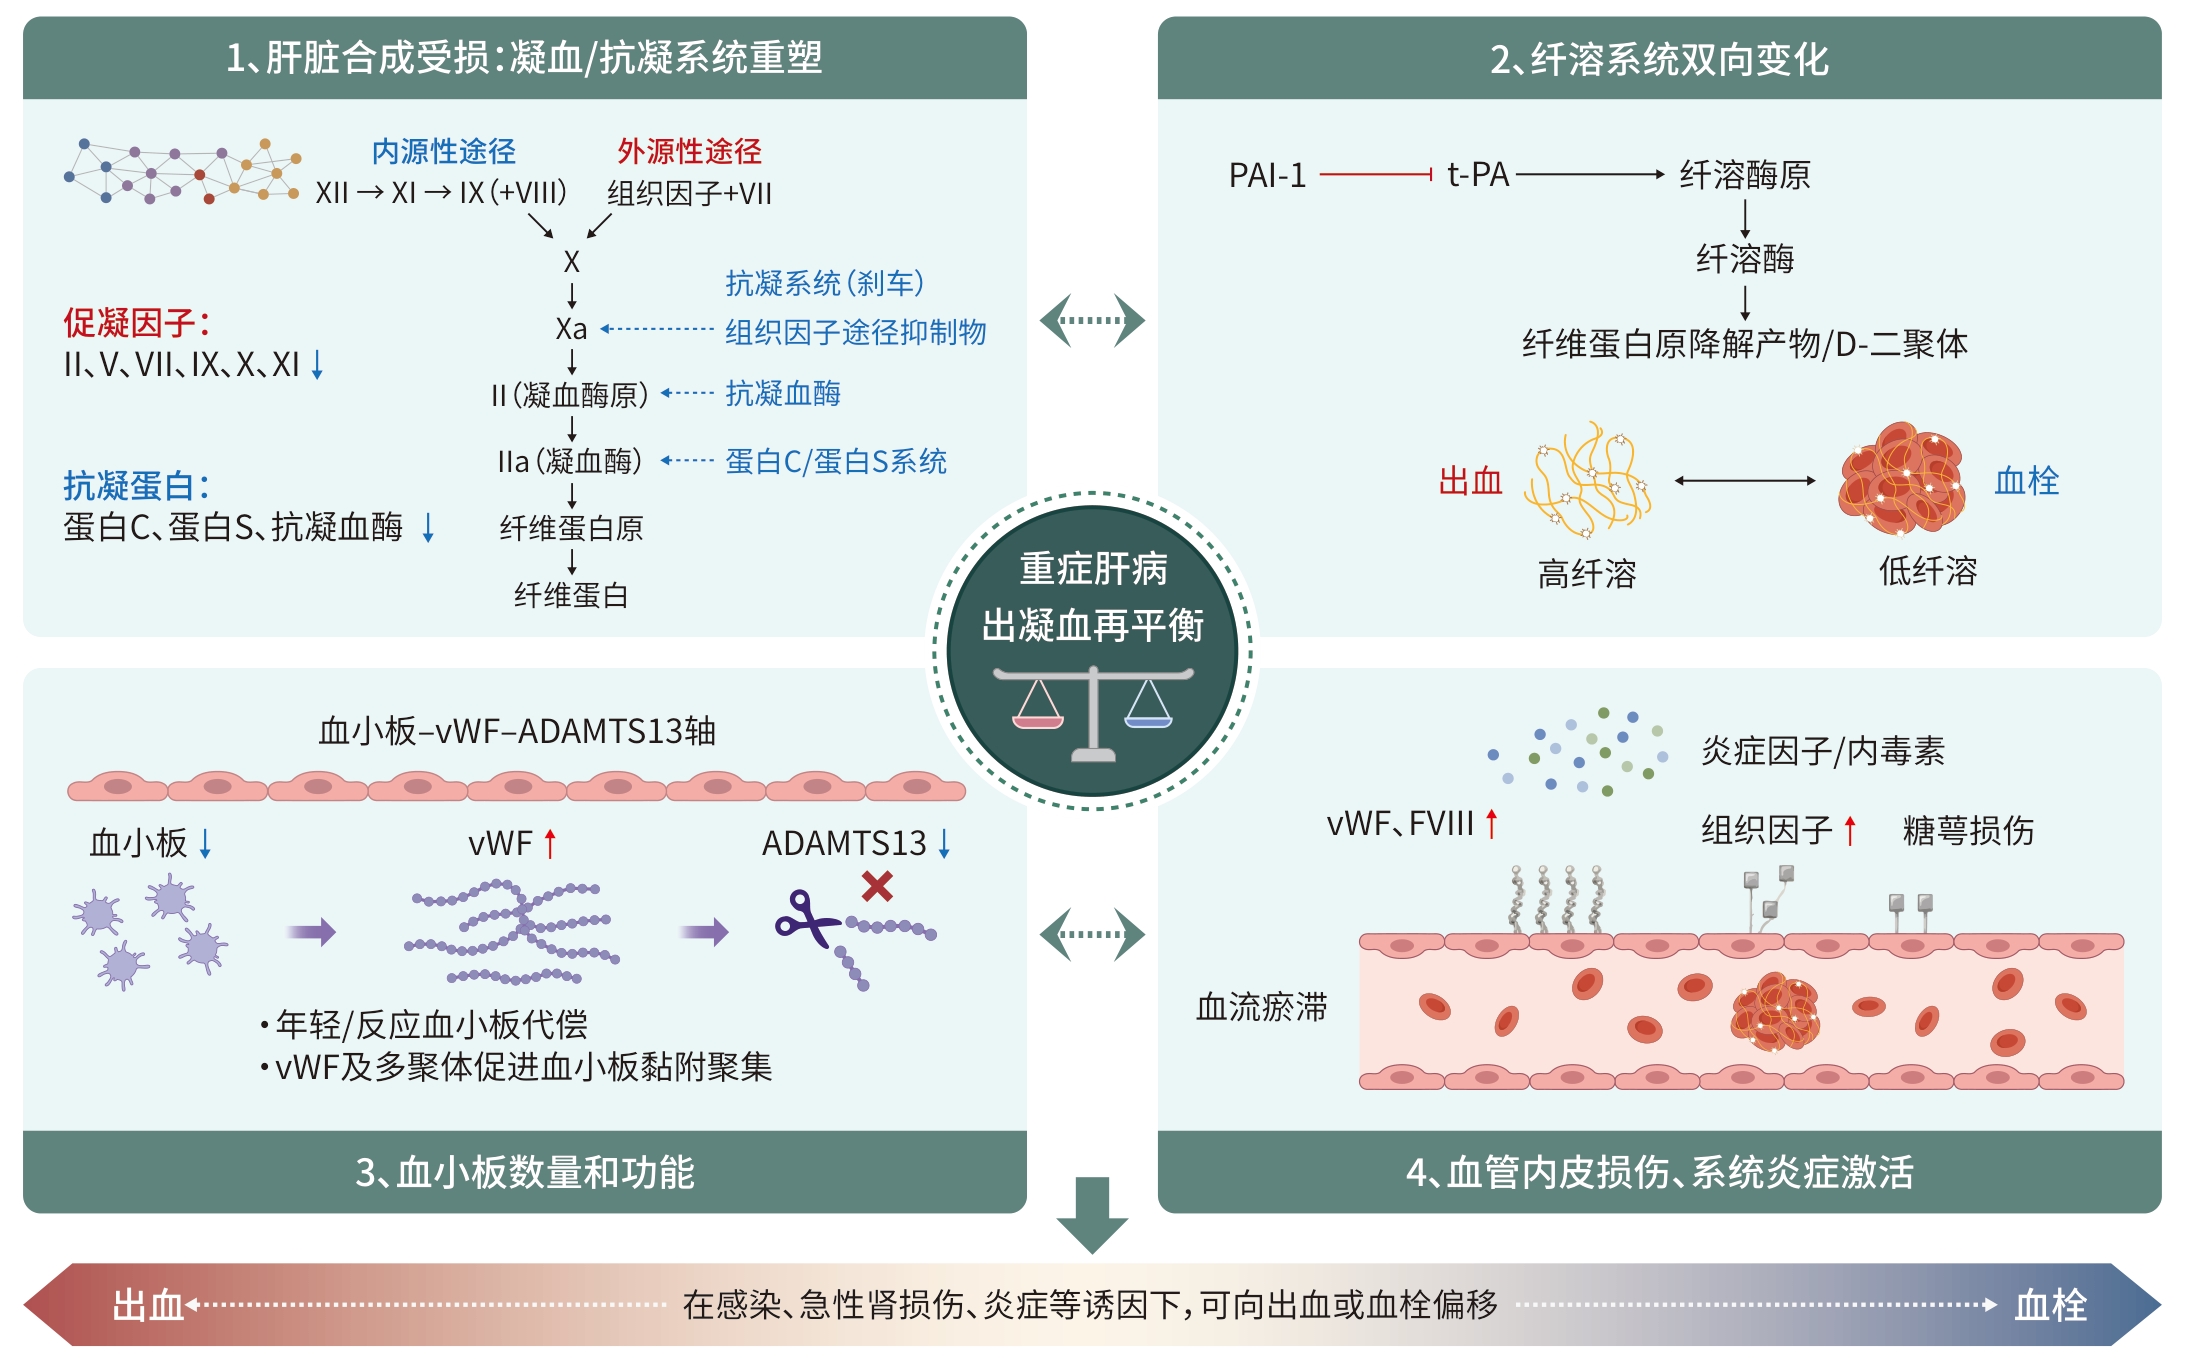
注: 重症肝病出凝血再平衡由血小板-内皮互作、vWF/ADAMTS13轴、促凝和抗凝因子同步下降、凝血酶生成、纤维蛋白结构及纤溶表型共同决定。感染、系统炎症、急性肾损伤、门静脉高压、侵入操作和输血等因素可使平衡向出血或血栓方向偏移。vWF,血管性血友病因子;ADAMTS13,血管性血友病因子裂解蛋白酶;FⅧ,凝血因子Ⅷ;t-PA,组织型纤溶酶原激活物;PAI-1,纤溶酶原激活物抑制物-1。
图 1 重症肝病出凝血再平衡机制示意图
Figure 1. Mechanisms of rebalanced hemostasis in severe liver disease
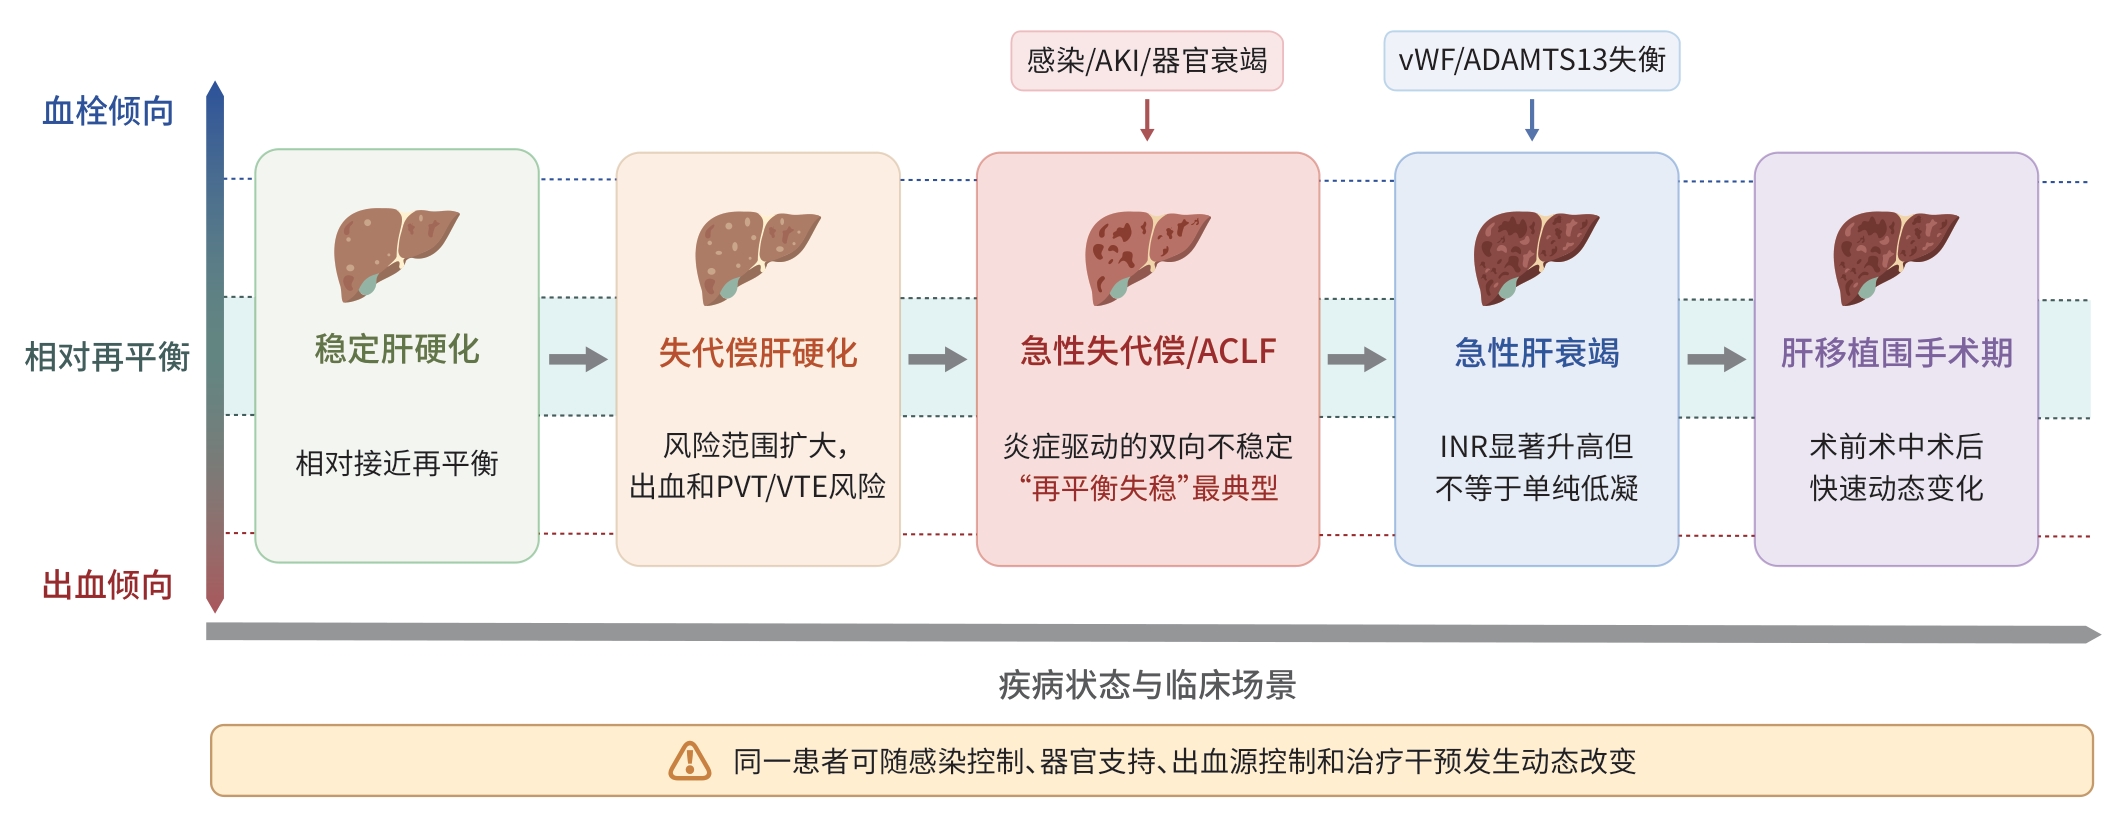
注: ACLF,慢加急性肝衰竭; INR,国际标准化比值; PVT,门静脉血栓形成;VTE,静脉血栓栓塞症;vWF,血管性血友病因子;ADAMTS13,血管性血友病因子裂解蛋白酶。
图 2 不同重症肝病状态下的出凝血再平衡特征
Figure 2. Spectrum of rebalanced hemostasis across different severe liver disease states
表 1 常规凝血指标在重症肝病中的意义与局限性
Table 1. Significance and limitations of conventional coagulation tests in severe liver disease
指标 临床意义 再平衡视角下的局限 使用建议 凝血酶原时间/国际
标准化比值、活化
部分凝血活酶时间反映部分促凝因子下降和
肝脏合成功能受损不能反映天然抗凝因子下降、血管性血友
病因子/血管性血友病因子裂解蛋白酶轴、
血小板黏附和纤溶状态可作基线和病情指标,不
能单独作为输血或排除血
栓依据血小板计数 提示初级止血底物不足和
脾功能亢进程度不能反映血小板功能、血管性血友病因子
代偿及剪切力条件下黏附能力结合出血史、操作风险和
黏弹性检测判断纤维蛋白原 提示存在凝块基质储备不
足,其水平降低与出血风
险升高相关不能完全代表凝块结构、聚合质量和抗纤
溶能力在存在活动性出血或实施
高风险操作时,应重点
评估D-二聚体 反映纤维蛋白形成/降解
增加或清除下降不能单独区分门静脉血栓形成/黏弹性检
测、炎症或纤溶方向需结合影像学和临床背景
解释 下载: 导出CSV
表 2 出凝血再平衡过程中促出血因素与促血栓因素
Table 2. Pro-bleeding and pro-thrombotic factors in rebalanced hemostasis
止血环节 促出血因素 促血栓因素 初级止血 血小板减少;
尿毒症毒素、高胆红素血症及感染相关血小板功能障碍vWF升高;ADAMTS13下降;高分子量vWF多聚体持续
存在;
代偿性的血小板功能亢进,黏附和活化增强凝血系统 促凝因子减少,包括凝血酶原及因子Ⅴ、Ⅶ、Ⅸ、Ⅹ、Ⅺ、XIII
下降;纤维蛋白原不足或凝块质量下降FⅧ相对保留或升高;天然抗凝因子下降,包括抗凝血酶、
蛋白C、蛋白S和TFPI下降纤溶系统 t-PA升高或清除减少;α2-抗纤溶酶、TAFI等纤溶抑制因
子下降;高纤溶导致凝块过早降解PAI-1升高;纤溶酶原减少;低纤溶或纤溶关闭;纤维蛋白
清除受限并促进微血栓形成注:vWF,血管性血友病因子;ADAMTS13,血管性血友病因子裂解蛋白酶;FⅧ,凝血因子Ⅷ;TFPI,组织因子途径抑制物;t-PA,组织型纤溶酶原激活物;TAFI,凝血酶激活的纤溶抑制物;PAI-1,纤溶酶原激活物抑制物-1。
下载: 导出CSV
-
[1] Roberts L N. Rebalanced hemostasis in liver disease: A misunderstood coagulopathy[J]. Hematology Am Soc Hematol Educ Program, 2021, 2021( 1): 485- 491. DOI: 10.1182/hematology.2021000283. [2] Lisman T, Caldwell S H, Intagliata N M. Haemostatic alterations and management of haemostasis in patients with cirrhosis[J]. J Hepatol, 2022, 76( 6): 1291- 1305. DOI: 10.1016/j.jhep.2021.11.004. [3] European Association for the Study of the Liver. EASL Clinical Practice Guidelines on prevention and management of bleeding and thrombosis in patients with cirrhosis[J]. J Hepatol, 2022, 76( 5): 1151- 1184. DOI: 10.1016/j.jhep.2021.09.003. [4] Northup P G, Garcia-Pagan J C, Garcia-Tsao G, et al. Vascular liver disorders, portal vein thrombosis, and procedural bleeding in patients with liver disease: 2020 practice guidance by the American Association for the Study of Liver Diseases[J]. Hepatology, 2021, 73( 1): 366- 413. DOI: 10.1002/hep.31646. [5] Lisman T, Porte R J. Rebalanced hemostasis in patients with liver disease: Evidence and clinical consequences[J]. Blood, 2010, 116( 6): 878- 885. DOI: 10.1182/blood-2010-02-261891. [6] Tripodi A, Mannucci P M. The coagulopathy of chronic liver disease[J]. N Engl J Med, 2011, 365( 2): 147- 156. DOI: 10.1056/NEJMra1011170. [7] National Clinical Research Center for Infectious Diseases; Society of Hepatology, Beijing Medical Association; Translational Medicine Branch, Chinese Association of Gerontology and Geriatrics. Expert consensus on the clinical diagnosis and treatment of coagulation disorders related to liver disease[J]. Chin J Hepatol, 2026, 34( 5): 417- 429. DOI: 10.3760/cma.j.cn501113-20260203-00055.国家感染性疾病临床医学研究中心, 北京医学会肝病学分会, 中国老年学和老年医学学会转化医学分会. 肝病相关凝血功能异常临床诊治专家共识[J]. 中华肝脏病杂志, 2026, 34( 5): 417- 429. DOI: 10.3760/cma.j.cn501113-20260203-00055. [8] Zermatten M G, Fraga M, Moradpour D, et al. Hemostatic alterations in patients with cirrhosis: From primary hemostasis to fibrinolysis[J]. Hepatology, 2020, 71( 6): 2135- 2148. DOI: 10.1002/hep.31201. [9] He Y L, Yao H J, Ageno W, et al. Review article: Thromboelastography in liver diseases[J]. Aliment Pharmacol Ther, 2022, 56( 4): 580- 591. DOI: 10.1111/apt.17080. [10] Campello E, Zanetto A, Bulato C, et al. Coagulopathy is not predictive of bleeding in patients with acute decompensation of cirrhosis and acute-on-chronic liver failure[J]. Liver Int, 2021, 41( 10): 2455- 2466. DOI: 10.1111/liv.15001. [11] Stravitz R T, Ellerbe C, Durkalski V, et al. Bleeding complications in acute liver failure[J]. Hepatology, 2018, 67( 5): 1931- 1942. DOI: 10.1002/hep.29694. [12] Intagliata N M, Argo C K, Stine J G, et al. Concepts and controversies in haemostasis and thrombosis associated with liver disease: Proceedings of the 7th international coagulation in liver disease conference[J]. Thromb Haemost, 2018, 118( 8): 1491- 1506. DOI: 10.1055/s-0038-1666861. [13] Takaya H, Namisaki T, Asada S, et al. ADAMTS13, VWF, and endotoxin are interrelated and associated with the severity of liver cirrhosis via hypercoagulability[J]. J Clin Med, 2022, 11( 7): 1835. DOI: 10.3390/jcm11071835. [14] Lisman T, Bongers T N, Adelmeijer J, et al. Elevated levels of von Willebrand Factor in cirrhosis support platelet adhesion despite reduced functional capacity[J]. Hepatology, 2006, 44( 1): 53- 61. DOI: 10.1002/hep.21231. [15] Carlin S, Cuker A, Gatt A, et al. Anticoagulation for stroke prevention in atrial fibrillation and treatment of venous thromboembolism and portal vein thrombosis in cirrhosis: Guidance from the SSC of the ISTH[J]. J Thromb Haemost, 2024, 22( 9): 2653- 2669. DOI: 10.1016/j.jtha.2024.05.023. [16] Mantaka A, Augoustaki A, Kouroumalis E A, et al. Portal vein thrombosis in cirrhosis: Diagnosis, natural history, and therapeutic challenges[J]. Ann Gastroenterol, 2018, 31( 3): 315- 329. DOI: 10.20524/aog.2018.0245. [17] Capece G E, Luyendyk J P, Poole L G. Fibrinolysis-mediated pathways in acute liver injury[J]. Semin Thromb Hemost, 2024, 50( 4): 638- 647. DOI: 10.1055/s-0044-1779738. [18] Blasi A, Patel V C, Adelmeijer J, et al. Mixed fibrinolytic phenotypes in decompensated cirrhosis and acute-on-chronic liver failure with hypofibrinolysis in those with complications and poor survival[J]. Hepatology, 2020, 71( 4): 1381- 1390. DOI: 10.1002/hep.30915. [19] El Otmani H, Stamouli M, Adelmeijer J, et al. Plasmin-mediated proteolysis of von Willebrand factor in patients with acute and chronic liver disease[J]. Res Pract Thromb Haemost, 2025, 9( 6): 103166. DOI: 10.1016/j.rpth.2025.103166. [20] Riescher-Tuczkiewicz A, Loyau S, Venisse L, et al. Platelet protease nexin-1 limits fibrinolysis in patients with cirrhosis[J]. JHEP Rep, 2025, 7( 12): 101563. DOI: 10.1016/j.jhepr.2025.101563. [21] de Franchis R, Bosch J, Garcia-Tsao G, et al. Baveno VII–Renewing consensus in portal hypertension[J]. J Hepatol, 2022, 76( 4): 959- 974. DOI: 10.1016/j.jhep.2021.12.022. [22] Basili S, Raparelli V, Napoleone L, et al. Platelet count does not predict bleeding in cirrhotic patients: Results from the PRO-LIVER study[J]. Am J Gastroenterol, 2018, 113( 3): 368- 375. DOI: 10.1038/ajg.2017.457. [23] Zhao F Z, Ding J N, Cui J J, et al. Platelet activation is upregulated in cirrhotic patients with portal vein thrombosis[J]. Thromb Haemost, 2024, 124( 8): 739- 752. DOI: 10.1055/a-2190-8705. [24] Uemura M, Fujimura Y, Matsumoto M, et al. Comprehensive analysis of ADAMTS13 in patients with liver cirrhosis[J]. Thromb Haemost, 2008, 99( 6): 1019- 1029. DOI: 10.1160/TH08-01-0006. [25] Hugenholtz G C G, Adelmeijer J, Meijers J C M, et al. An unbalance between von Willebrand factor and ADAMTS13 in acute liver failure: Implications for hemostasis and clinical outcome[J]. Hepatology, 2013, 58( 2): 752- 761. DOI: 10.1002/hep.26372. [26] Tripodi A, Primignani M, Chantarangkul V, et al. Thrombin generation in patients with cirrhosis: The role of platelets[J]. Hepatology, 2006, 44( 2): 440- 445. DOI: 10.1002/hep.21266. [27] Engelmann C, Clària J, Szabo G, et al. Pathophysiology of decompensated cirrhosis: Portal hypertension, circulatory dysfunction, inflammation, metabolism and mitochondrial dysfunction[J]. J Hepatol, 2021, 75( Suppl 1): S49- S66. DOI: 10.1016/j.jhep.2021.01.002. [28] Campello E, Zanetto A, Ferdinande K, et al. Extracellular vesicles reflect thrombo-inflammatory, endothelial and tissue-remodelling changes in cirrhosis[J]. Liver Int, 2026, 46( 7): e70723. DOI: 10.1111/liv.70723. [29] Blasi A, Calvo A, Prado V, et al. Coagulation failure in patients with acute-on-chronic liver failure and decompensated cirrhosis: Beyond the international normalized ratio[J]. Hepatology, 2018, 68( 6): 2325- 2337. DOI: 10.1002/hep.30103. [30] Fisher C, Patel V C, Stoy S H, et al. Balanced haemostasis with both hypo- and hyper-coagulable features in critically ill patients with acute-on-chronic-liver failure[J]. J Crit Care, 2018, 43: 54- 60. DOI: 10.1016/j.jcrc.2017.07.053. [31] de Pietri L, Bianchini M, Montalti R, et al. Thrombelastography-guided blood product use before invasive procedures in cirrhosis with severe coagulopathy: A randomized, controlled trial[J]. Hepatology, 2016, 63( 2): 566- 573. DOI: 10.1002/hep.28148. [32] Buliarca A, Horhat A, Mocan T, et al. Viscoelastic tests in liver disease: Where do we stand now?[J]. World J Gastroenterol, 2021, 27( 23): 3290- 3302. DOI: 10.3748/wjg.v27.i23.3290. [33] Villa E, Cammà C, Marietta M, et al. Enoxaparin prevents portal vein thrombosis and liver decompensation in patients with advanced cirrhosis[J]. Gastroenterology, 2012, 143( 5): 1253- 1260.e4. DOI: 10.1053/j.gastro.2012.07.018. [34] Davis J P E, Lim J K, Francis F F, et al. AGA clinical practice update on management of portal vein thrombosis in patients with cirrhosis: Expert review[J]. Gastroenterology, 2025, 168( 2): 396- 404.e1. DOI: 10.1053/j.gastro.2024.10.038. [35] Wang L, Guo X Z, Xu X B, et al. Anticoagulation favors thrombus recanalization and survival in patients with liver cirrhosis and portal vein thrombosis: Results of a meta-analysis[J]. Adv Ther, 2021, 38( 1): 495- 520. DOI: 10.1007/s12325-020-01550-4. [36] Stevens S M, Woller S C, Kreuziger L B, et al. Antithrombotic therapy for VTE disease: Second update of the CHEST guideline and expert panel report[J]. Chest, 2021, 160( 6): e545- e608. DOI: 10.1016/j.chest.2021.07.055. [37] Baskin J L, Pui C H, Reiss U, et al. Management of occlusion and thrombosis associated with long-term indwelling central venous catheters[J]. Lancet, 2009, 374( 9684): 159- 169. DOI: 10.1016/S0140-6736(09)60220-8. [38] Rajasekhar A, Streiff M B. How I treat central venous access device-related upper extremity deep vein thrombosis[J]. Blood, 2017, 129( 20): 2727- 2736. DOI: 10.1182/blood-2016-08-693671. -

 本文二维码
计量
- 文章访问数: 17
- HTML全文浏览量: 7
- PDF下载量: 0
- 被引次数: 0


