

 PDF下载 ( 1657 KB)

弥散性血管内凝血与肝硬化凝血功能障碍:鉴别误区与临床对策
DOI: 10.12449/JCH260903
Disseminated intravascular coagulation versus cirrhosis-associated coagulopathy: Diagnostic challenges and clinical strategies
-
摘要: 肝硬化患者的止血功能状态并非单纯处于低凝状态,而是促凝系统、抗凝系统、血管性血友病因子-血小板轴及纤溶系统发生同步重塑后形成的脆弱再平衡状态。肝硬化患者常存在血小板减少、凝血酶原时间/国际标准化比值延长、纤维蛋白原异常及D-二聚体升高等实验室检查结果异常,上述表现与弥散性血管内凝血(DIC)存在高度重叠,临床容易发生误诊,进而导致不必要的血制品输注或凝血指标纠正干预。现有研究证据显示,因子Ⅷ水平及通用国际血栓与止血学会DIC评分在肝病患者中的鉴别诊断价值有限,目前尚无统一的鉴别诊断路径。本文围绕肝硬化止血再平衡与DIC病理生理机制的交叉部分,系统梳理了常规凝血指标、新型止血标志物及整体止血检测在二者鉴别诊断中的应用价值,并结合感染、急性失代偿、消化道出血、肝细胞癌及围手术期等特殊临床场景,提出了“诱因识别-基线对比-动态监测-器官评估”的四步诊断路径。未来需建立基于肝病特征的DIC预测模型,结合黏弹性检测与多维度生物标志物,实现肝硬化患者凝血异常的精准风险分层与个体化管理。Abstract: The hemostatic function in patients with liver cirrhosis is not simply in a state of hypocoagulability, but rather a fragile rebalanced state resulting from the simultaneous remodeling of procoagulant and anticoagulant systems, the von Willebrand factor-platelet axis, and the fibrinolytic system. Since patients with liver cirrhosis frequently exhibit laboratory abnormalities including thrombocytopenia, prolonged prothrombin time/international normalized ratio, abnormal fibrinogen level, and elevated D-dimer, these manifestations substantially overlap with the laboratory phenotype of disseminated intravascular coagulation (DIC), leading to potential misdiagnosis and unnecessary blood product transfusion or correction of coagulation parameters in clinical practice. Current evidence suggests that factor Ⅷ level and the widely used International Society on Thrombosis and Haemostasis DIC scoring system have limited value in differential diagnosis in patients with liver disease, and there is still a lack of a unified pathway for differential diagnosis. This article systematically reviews the pathophysiological overlap between rebalanced hemostasis in liver cirrhosis and DIC and summarizes the diagnostic value of conventional coagulation parameters, emerging hemostatic biomarkers, and global hemostatic assays in differential diagnosis of these conditions. Furthermore, it proposes a four-step diagnostic pathway of “trigger identification, baseline comparison, dynamic monitoring, and organ assessment” with reference to the specific clinical scenarios including infection, acute decompensation, gastrointestinal bleeding, hepatocellular carcinoma, and the perioperative period. In the future, DIC prediction models based on the features of liver disease should be established in combination with viscoelastic testing and multidimensional biomarkers, so as to achieve precise risk stratification and individualized management of coagulation abnormalities in patients with liver cirrhosis.
-

图 1 肝硬化患者疑似弥散性血管内凝血的分层鉴别诊断路径
Figure 1. A stepwise diagnostic pathway for suspected disseminated intravascular coagulation in patients with cirrhosis
注: DIC,弥散性血管内凝血。
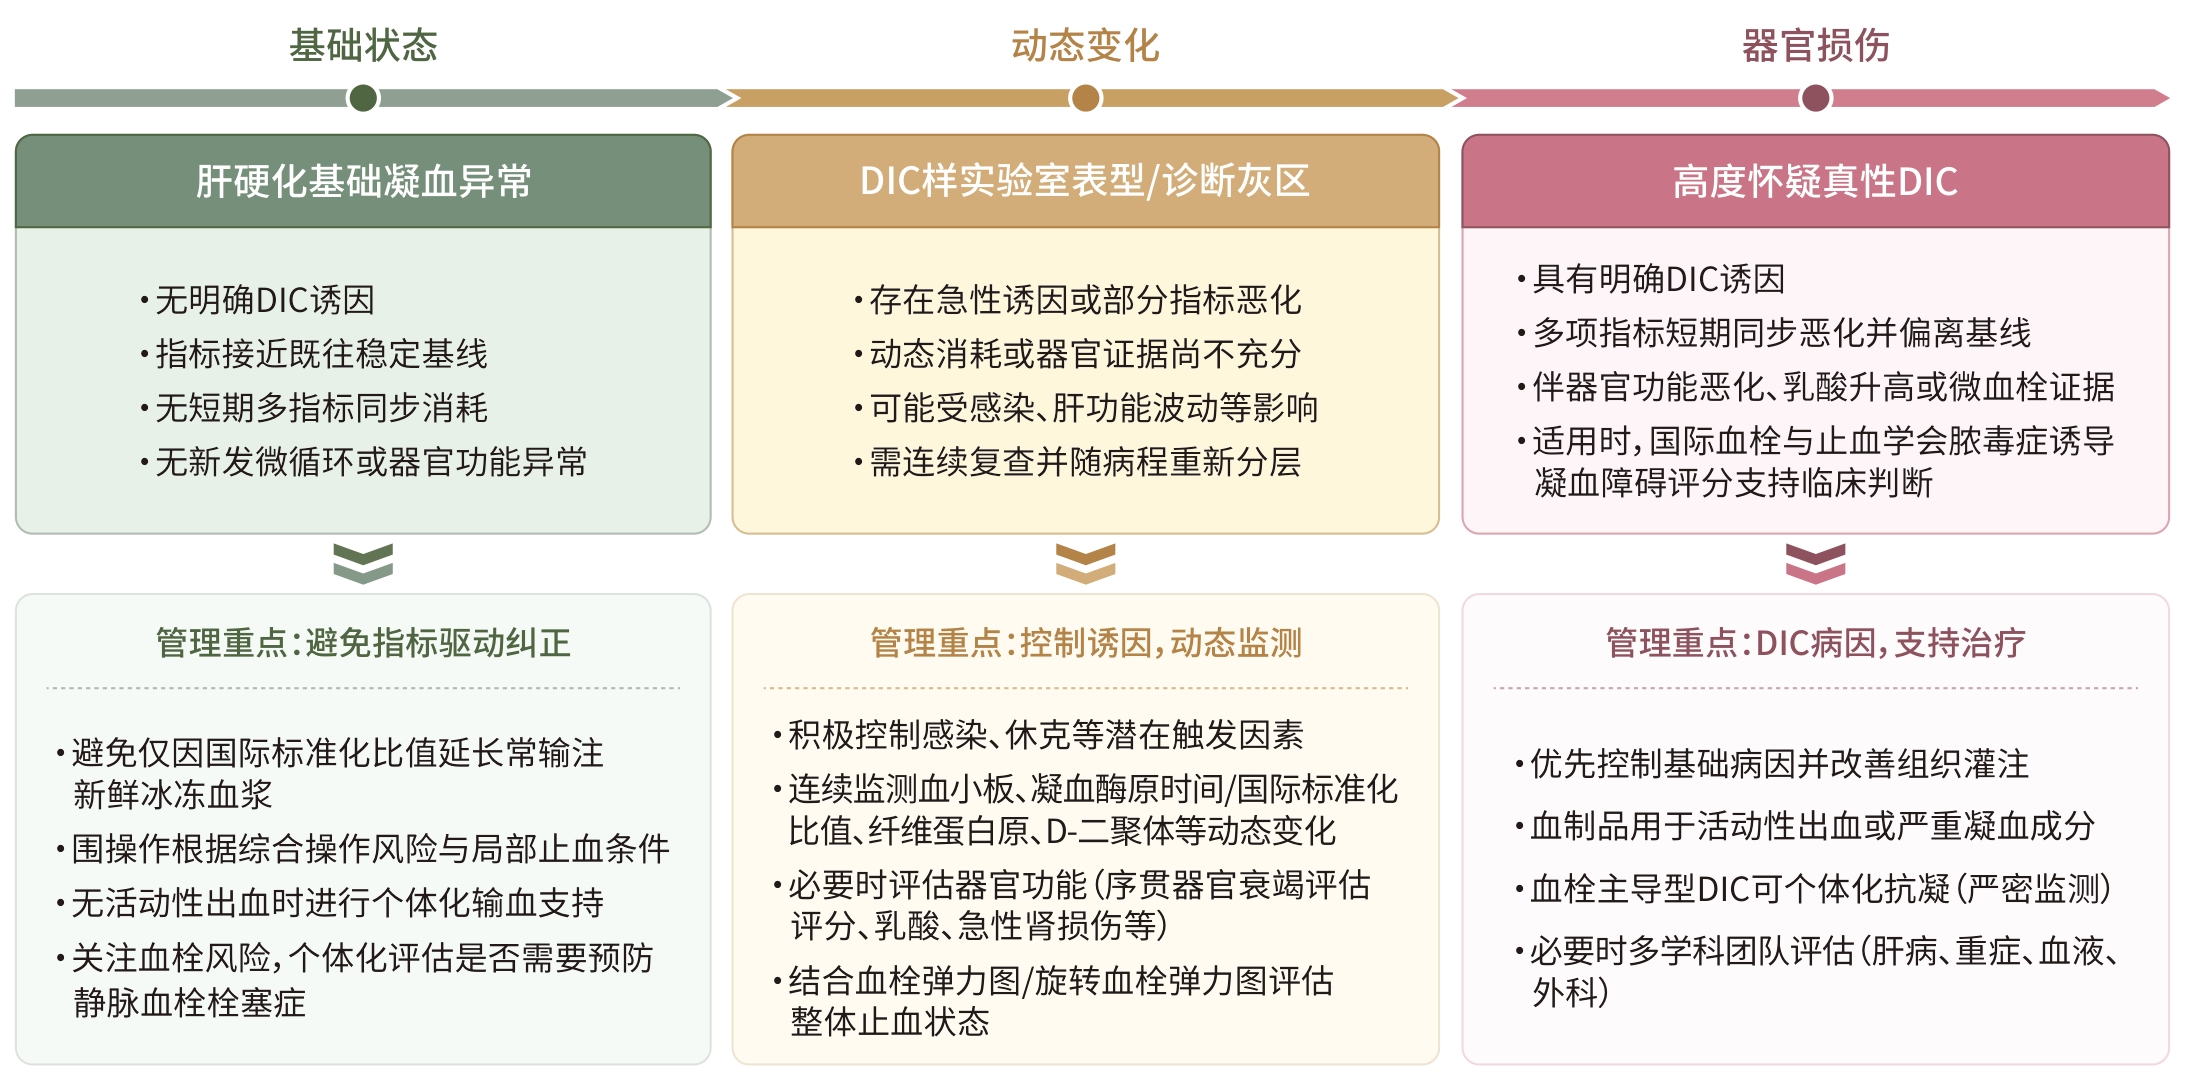
图 2 肝硬化相关凝血异常与DIC的综合分层判断及管理策略
Figure 2. Integrated risk stratification and management strategies for cirrhosis-associated coagulopathy and DIC
表 1 DIC与肝硬化相关凝血功能障碍常用指标比较
Table 1. Comparison of commonly used indicators in DIC and cirrhosis-associated coagulopathy
指标 肝硬化相关凝血障碍 DIC 鉴别线索 血小板 慢性降低常见,机制包括脾功能亢
进、TPO减少、骨髓抑制及感染等;
vWF升高可部分代偿黏附功能凝血激活和微血栓形成导致消耗性
降低,常呈进行性下降短期快速下降或较基线明显下降更
支持DIC/SICPT/INR、APTT 反映促凝因子合成下降,但不能反
映天然抗凝蛋白同步下降;不能单
独预测出血风险反映消耗性凝血因子减少、凝血激活
后失代偿与基线相比进行性延长,并伴器官功
能恶化更支持DIC纤维蛋白原 稳定期可正常或升高;晚期、ACLF
或急性事件中可降低;还可存在获
得性异常纤维蛋白原血症典型消耗性降低;但脓毒症早期可因
急性期反应正常或升高短期持续下降,尤其与血小板下降和
D-二聚体升高同步,更支持DICD-二聚体/FDP 常升高,受纤维蛋白周转、炎症、门
静脉血流和肝清除下降影响常升高,反映凝血和继发纤溶激活,
是评分核心变量绝对值阈值缺乏肝病特异性;动态陡
升及器官功能恶化更有意义因子Ⅴ 常因肝合成下降而降低 可因消耗而降低 单独鉴别价值有限;可作为多指标模
型的一部分因子Ⅷ 多因内皮激活、vWF升高和清除下
降而升高可因消耗下降,也可因炎症和内皮激
活升高不能作为独立鉴别指标;动态和组合
模型可能更有价值抗凝血酶、蛋
白C、蛋白S常因肝合成下降而降低,构成再平
衡的一部分可因消耗、内皮损伤和炎症进一步
降低急性进一步下降可提示DIC/SIC,但
受基础肝病限制vWF/
ADAMTS13vWF升高、ADAMTS13下降常见,
提示内皮激活和血小板黏附代偿vWF升高也可见于DIC/脓毒症内皮
损伤更适合机制分型,尚不能单独确诊
DICTEG/ROTEM 可显示整体凝块形成、强度和纤溶
状态,部分患者与常规指标不一致可显示凝块形成迟缓、强度降低或纤
溶异常,受DIC阶段影响适合辅助输血和整体止血评估,但仍
需结合临床注:DIC,弥散性血管内凝血;SIC,脓毒症诱导的凝血病;TPO,血小板生成素;vWF,血管性血友病因子;ADAMTS13,血管性血友病因子裂解蛋白酶;PT,凝血酶原时间;INR,国际标准化比值;APTT,活化部分凝血活酶时间;ACLF,慢加急性肝衰竭;FDP,纤维蛋白降解产物;TEG,血栓弹力图;ROTEM,旋转血栓弹力图。
 下载: 导出CSV
表 2 特殊临床场景下肝硬化患者DIC鉴别要点
Table 2. Key points for differentiating DIC in cirrhotic patients in special clinical scenarios
临床场景 混淆原因 更支持肝硬化相关
凝血异常更支持合并DIC 临床处理重点 感染[9,23,27]/
脓毒症[11,16,28]炎症导致D-二聚体
升高、血小板下降、
INR延长感染控制后指标逐渐
恢复;无进行性消耗血小板快速下降、纤维蛋
白原降低、D-二聚体持续
升高、器官功能恶化SIC用于风险识别,结合动态变
化判断急性失代偿[5]/
ACLF[24]肝功能恶化、炎症
反应均可影响凝血
指标与既往肝功能储备下
降一致急性消耗性改变,伴急性
肾损伤、休克、多器官衰竭重点评估诱因及器官衰竭进展 急性肝衰竭[24,29] INR明显升高,类似
DIC单纯肝合成功能衰竭 感染、休克、血小板下降及
微血栓相关损伤INR不能单独诊断DIC 消化道出血[15,30-34] 失血、输血、休克造
成凝血指标异常出血控制后恢复 持续凝血恶化、感染或休
克背景下DIC表现治疗门静脉高压出血,而非纠正
INR肝细胞癌[6,13,35] 肿瘤高凝和DIC均
可升高D-二聚体稳定肿瘤相关高凝
状态感染、介入治疗后出现消
耗性凝血障碍区分慢性高凝与急性DIC 肝移植围手术期[36] 无肝期、再灌注、输
血导致指标异常随移植物功能恢复
改善持续恶化并伴感染、移植
物功能障碍、多器官损伤血栓弹力图/旋转血栓弹力图指
导输血,不宜单纯依据国际血栓
与止血学会评分诊断DIC注:DIC,弥散性血管内凝血;SIC,脓毒症诱导的凝血病;ACLF,慢加急性肝衰竭;INR,国际标准化比值。
下载: 导出CSV
表 3 肝硬化患者凝血异常及疑似DIC的管理建议
Table 3. Management recommendations for patients with liver cirrhosis presenting with coagulation abnormalities and suspected DIC
临床场景 常见误区 推荐策略 稳定肝硬化、低风险
操作前仅因INR升高常规输注新鲜冰冻血浆,
将INR纠正作为操作前目标评估操作风险、既往出血史及肝病状态;多数低风险操
作无需纠正INR血小板减少 仅依据血小板计数降低进行预防性输注 结合操作类型、活动性出血、肝癌及血栓风险个体化处
理;必要时考虑血小板输注或血小板生成素受体激
动剂低纤维蛋白原 非出血状态下经验性补充纤维蛋白原制剂 活动性出血、高风险操作或黏弹性止血试验提示凝块
形成能力下降时考虑补充感染/ACLF伴凝血异常 将感染相关凝血改变直接诊断为DIC 明确感染诱因,比较基线资料,动态监测血小板、PT/
INR、纤维蛋白原及D-二聚体变化,并评估器官功能疑似DIC 仅依据国际血栓与止血学会DIC评分达到
阈值诊断DIC结合诱因、基线变化、动态消耗及器官损伤综合判断 住院血栓预防 因INR升高或血小板减少机械性排除静脉
血栓栓塞症的预防根据静脉血栓栓塞症风险、活动性出血及肝病严重程
度决定药物或机械预防并发DIC 仅补充凝血因子而忽视基础疾病 优先治疗感染、休克、肿瘤等诱因;血制品用于活动性
出血或严重凝血成分缺乏注:DIC,弥散性血管内凝血;INR,国际标准化比值;ACLF,慢加急性肝衰竭;PT,凝血酶原时间。
下载: 导出CSV
-
[1] Lisman T, Hernandez-Gea V, Magnusson M, et al. The concept of rebalanced hemostasis in patients with liver disease: Communication from the ISTH SSC working group on hemostatic management of patients with liver disease[J]. J Thromb Haemost, 2021, 19( 4): 1116- 1122. DOI: 10.1111/jth.15239. [2] Lisman T, Caldwell S H, Intagliata N M. Haemostatic alterations and management of haemostasis in patients with cirrhosis[J]. J Hepatol, 2022, 76( 6): 1291- 1305. DOI: 10.1016/j.jhep.2021.11.004. [3] European Association for the Study of the Liver. EASL Clinical Practice Guidelines on prevention and management of bleeding and thrombosis in patients with cirrhosis[J]. J Hepatol, 2022, 76( 5): 1151- 1184. DOI: 10.1016/j.jhep.2021.09.003. [4] O’Leary J G, Greenberg C S, Patton H M, et al. AGA clinical practice update: Coagulation in cirrhosis[J]. Gastroenterology, 2019, 157( 1): 34- 43. e 1. DOI: 10.1053/j.gastro.2019.03.070. [5] Zanetto A, Northup P, Roberts L, et al. Haemostasis in cirrhosis: Understanding destabilising factors during acute decompensation[J]. J Hepatol, 2023, 78( 5): 1037- 1047. DOI: 10.1016/j.jhep.2023.01.010. [6] Northup P G, Garcia-Pagan J C, Garcia-Tsao G, et al. Vascular liver disorders, portal vein thrombosis, and procedural bleeding in patients with liver disease: 2020 practice guidance by the American Association for the Study of Liver Diseases[J]. Hepatology, 2021, 73( 1): 366- 413. DOI: 10.1002/hep.31646. [7] Tapper E B, Parikh N D. Diagnosis and management of cirrhosis and its complications: A review[J]. Jama, 2023, 329( 18): 1589. DOI: 10.1001/jama.2023.5997. [8] Ginès P, Krag A, Abraldes J G, et al. Liver cirrhosis[J]. Lancet, 2021, 398( 10308): 1359- 1376. DOI: 10.1016/S0140-6736(21)01374-X. [9] Zanetto A, Campello E, Bulato C, et al. Global hemostatic profiling in patients with decompensated cirrhosis and bacterial infections[J]. JHEP Rep, 2022, 4( 7): 100493. DOI: 10.1016/j.jhepr.2022.100493. [10] Gando S, Levi M, Toh C H. Disseminated intravascular coagulation[J]. J Intensive Care, 2025, 13( 1): 32. DOI: 10.1186/s40560-025-00794-y. [11] Iba T, Levy J H, Yamakawa K, et al. Proposal of a two-step process for the diagnosis of sepsis-induced disseminated intravascular coagulation[J]. J Thromb Haemost, 2019, 17( 8): 1265- 1268. DOI: 10.1111/jth.14482. [12] Roberts L N, Hernandez‐Gea V, Magnusson M, et al. Thromboprophylaxis for venous thromboembolism prevention in hospitalized patients with cirrhosis: Guidance from the SSC of the ISTH[J]. J Thromb Haemost, 2022, 20( 10): 2237- 2245. DOI: 10.1111/jth.15829. [13] Davis J P E, Lim J K, Francis F F, et al. AGA clinical practice update on management of portal vein thrombosis in patients with cirrhosis: Expert review[J]. Gastroenterology, 2025, 168( 2): 396- 404.e1. DOI: 10.1053/j.gastro.2024.10.038. [14] Roberts L N, Lisman T, Stanworth S, et al. Periprocedural management of abnormal coagulation parameters and thrombocytopenia in patients with cirrhosis: Guidance from the SSC of the ISTH[J]. J Thromb Haemost, 2022, 20( 1): 39- 47. DOI: 10.1111/jth.15562. [15] de Franchis R, Bosch J, Garcia-Tsao G, et al. Baveno VII–Renewing consensus in portal hypertension[J]. J Hepatol, 2022, 76( 4): 959- 974. DOI: 10.1016/j.jhep.2021.12.022. [16] Iba T, Nisio M D, Levy J H, et al. New criteria for sepsis-induced coagulopathy(SIC) following the revised sepsis definition: A retrospective analysis of a nationwide survey[J]. BMJ Open, 2017, 7( 9): e017046. DOI: 10.1136/bmjopen-2017-017046. [17] Iba T, Levy J H, Maier C L, et al. Updated definition and scoring of disseminated intravascular coagulation in 2025: Communication from the ISTH SSC Subcommittee on Disseminated Intravascular Coagulation[J]. J Thromb Haemost, 2025, 23( 7): 2356- 2362. DOI: 10.1016/j.jtha.2025.03.038. [18] Thrombosis and Hemostasis Group, Chinese Society of Hematology, Chinese Medical Association. Consensus of Chinese experts on diagnosis of disseminated intravascular coaguiation(version 2017)[J]. Chin J Hematol, 2017, 38( 5): 361- 363. DOI: 10.3760/cma.j.issn.0253-2727.2017.05.001.中华医学会血液学分会血栓与止血学组. 弥散性血管内凝血诊断中国专家共识(2017年版)[J]. 中华血液学杂志, 2017, 38( 5): 361- 363. DOI: 10.3760/cma.j.issn.0253-2727.2017.05.001. [19] Taylor F B Jr, Toh C H, Hoots W K, et al. Towards definition, clinical and laboratory criteria, and a scoring system for disseminated intravascular coagulation[J]. Thromb Haemost, 2001, 86( 5): 1327- 1330. [20] Levi M, Toh C H, Thachil J, et al. Guidelines for the diagnosis and management of disseminated intravascular coagulation. British Committee for Standards in Haematology[J]. Br J Haematol, 2009, 145( 1): 24- 33. DOI: 10.1111/j.1365-2141.2009.07600.x. [21] Zanetto A, Campello E, Bulato C, et al. Whole blood thrombin generation shows a significant hypocoagulable state in patients with decompensated cirrhosis[J]. J Thromb Haemost, 2024, 22( 2): 480- 492. DOI: 10.1016/j.jtha.2023.10.008. [22] Allen C, Heskel M, Butt A, et al. Factor VIII levels and ISTH disseminated intravascular coagulation scores do not distinguish disseminated intravascular coagulation from the coagulopathy of liver disease[J]. Acta Haematol, 2025, 148( 2): 220- 225. DOI: 10.1159/000540239. [23] Bajaj J S, Kamath P S, Reddy K R. The evolving challenge of infections in cirrhosis[J]. N Engl J Med, 2021, 384( 24): 2317- 2330. DOI: 10.1056/NEJMra2021808. [24] European Association for the Study of the Liver. EASL Clinical Practice Guidelines on acute-on-chronic liver failure[J]. J Hepatol, 2023, 79( 2): 461- 491. DOI: 10.1016/j.jhep.2023.04.021. [25] Xu X Y, Guan Y J, Xu J H, et al. Chinese expert consensus for the management of thrombocytopenia in cirrhosis[J]. J Clin Transl Hepatol, 2025, 13( 6): 516- 523. DOI: 10.14218/JCTH.2025.00105. [26] Balaceanu L A, Dina I. D-dimers in advanced liver cirrhosis: Useful biomarker or not[J]. Am J Med Sci, 2024, 368( 5): 415- 423. DOI: 10.1016/j.amjms.2024.05.017. [27] Biggins S W, Angeli P, Garcia-Tsao G, et al. Diagnosis, evaluation, and management of ascites, spontaneous bacterial peritonitis and hepatorenal syndrome: 2021 practice guidance by the American Association for the Study of Liver Diseases[J]. Hepatology, 2021, 74( 2): 1014- 1048. DOI: 10.1002/hep.31884. [28] Chinese College of Emergency Physicians, Chinese Medical Doctor Association; Shock and Sepsis Professional Committee, Chinese Research Hospital Association. Chinese emergency guidelines for sepsis and septic shock(2018)[J]. J Clin Emerg, 2018, 19( 9): 567- 576. DOI: 10.1321/j.issn.1009-5917.2018.09.001.中国医师协会急诊医师分会, 中国研究型医院学会休克与脓毒症专业委员会. 中国脓毒症/脓毒性休克急诊治疗指南(2018)[J]. 临床急诊杂志, 2018, 19( 9): 567- 588. DOI: 10.13201/j.issn.1009-5918.2018.09.001. [29] Liver Failure and Artificial Liver Group, Chinese Society of Infectious Diseases, Chinese Medical Association; Severe Liver Disease and Artificial Liver Group, Chinese Society of Hepatology, Chinese Medical Association. Guideline for diagnosis and treatment of liver failure(2024 version)[J]. J Clin Hepatol, 2024, 40( 12): 2371- 2387. DOI: 10.12449/JCH241206.中华医学会感染病学分会肝衰竭与人工肝学组, 中华医学会肝病学分会重型肝病与人工肝学组. 肝衰竭诊治指南(2024年版)[J]. 临床肝胆病杂志, 2024, 40( 12): 2371- 2387. DOI: 10.12449/JCH241206. [30] Chinese Society of Hepatology, Chinese Society of Gastroenterology, Chinese Society of Digestive Endoscopology, Chinese Medical Association. Guidelines for prevention and treatment of esophagogastric variceal bleeding in cirrhosis(2023)[J]. J Clin Hepatol, 2023, 39( 3): 527- 538. DOI: 10.3760/cma.j.cn501113-20220824-00436.中华医学会肝病学分会, 中华医学会消化病学分会, 中华医学会消化内镜学分会. 肝硬化门静脉高压食管胃静脉曲张出血的防治指南[J]. 临床肝胆病杂志, 2023, 39( 3): 527- 538. DOI: 10.3760/cmaj.cn501113-20220824-00436. [31] Spleen and Portal Hypertension Surgery Group, Chinese Society of Surgery, Chinese Medical Association. Expert consensus on diagnosis and treatment of esophagogastric variceal bleeding in cirrhosis(2025)[J]. Chin J Dig Surg, 2025, 24( 3): 271- 280. DOI: 10.3760/cma.j.cn115610-20241228-00590.中华医学会外科学分会脾及门静脉高压外科学组. 肝硬化门静脉高压症食管、胃底静脉曲张破裂出血诊治专家共识(2025版)[J]. 中华消化外科杂志, 2025, 24( 3): 271- 280. DOI: 10.3760/cma.j.cn115610-20241228-00590. [32] Kaplan D E, Ripoll C, Thiele M, et al. AASLD Practice Guidance on risk stratification and management of portal hypertension and varices in cirrhosis[J]. Hepatology, 2024, 79( 5): 1180- 1211. DOI: 10.1097/HEP.0000000000000647. [33] Rout G, Shalimar, Gunjan D, et al. Thromboelastography-guided blood product transfusion in cirrhosis patients with variceal bleeding: A randomized controlled trial[J]. J Clin Gastroenterol, 2020, 54( 3): 255- 262. DOI: 10.1097/MCG.0000000000001214. [34] Kumar M, Ahmad J, Maiwall R, et al. Thromboelastography-guided blood component use in patients with cirrhosis with nonvariceal bleeding: A randomized controlled trial[J]. Hepatology, 2020, 71( 1): 235- 246. DOI: 10.1002/hep.30794. [35] Reig M, Forner A, Rimola J, et al. BCLC strategy for prognosis prediction and treatment recommendation: The 2022 update[J]. J Hepatol, 2022, 76( 3): 681- 693. DOI: 10.1016/j.jhep.2021.11.018. [36] Perioperative Management Group, Chinese Society of Organ Transplantation, Chinese Medical Association. Expert consensus on perioperative coagulation management in adult liver transplant recipients(2026 edition)[J]. Chin J Surg, 2026, 64( 3): 191- 198. DOI: 10.3760/cma.j.cn112139-20251013-00468.中华医学会器官移植学分会围手术期管理学组. 成人肝移植受者围手术期凝血功能管理指南(2026 版)[J]. 中华外科杂志, 2026, 64( 3): 191- 198. DOI: 10.3760/cma.j.cn112139-20251013-00468. [37] Chinese Society of Hepatology, Chinese Medical Association. Clinical practice guidelines for diagnosis and treatment of cirrhosis(2025 edition)[J]. Chin J Hepatol, 2025, 33( 10): 958- 976. DOI: 10.3760/cma.j.cn501113-20250728-00298.中华医学会肝病学分会. 肝硬化临床诊治管理指南(2025版)[J]. 中华肝脏病杂志, 2025, 33( 10): 958- 976. DOI: 10.3760/cma.j.cn501113-20250728-00298. [38] Hepatobiliary Disease Group, Chinese Society of Gastroenterology. Expert consensus on portal vein thrombosis management in cirrhosis(Shanghai 2020)[J]. J Clin Hepatol, 2020, 36( 12): 2667- 2674. DOI: 10.3969/j.issn.1001-5256.2020.12.007.中华医学会消化病学分会肝胆疾病学组. 肝硬化门静脉血栓管理专家共识(2020年,上海)[J]. 临床肝胆病杂志, 2020, 36( 12): 2667- 2674. DOI: 10.3969/j.issn.1001-5256.2020.12.007. -

 本文二维码
计量
- 文章访问数: 18
- HTML全文浏览量: 8
- PDF下载量: 0
- 被引次数: 0


